8 Powerful Truths Moxifloxacin Life-Saving Antibiotic or Dangerous Side Effects?
Moxifloxacin Life-Saving Antibiotic or Dangerous Side Effects? 7 Truths!
Why can the same antibiotic pull a patient back from the edge of a life-threatening infection yet send another patient to the emergency room with a cardiac arrhythmia? The answer does not live on the pharmacy shelf. It lives in the drug’s pharmacology, its spectrum, the patient’s baseline risk, and the prescriber’s ability to weigh benefit against harm. Moxifloxacin belongs to a class that clinicians respect and fear in almost equal measure. It is not a first-line agent for uncomplicated infections. It is a reserve weapon for specific, often severe or resistant clinical situations. Yet its reputation carries a shadow: fluoroquinolone toxicity. This article dissects moxifloxacin under a clinical microscope. We will walk through FDA-approved indications, mechanism, pharmacokinetics, drug interactions, cardiac risks, nerve damage, pregnancy and lactation data, dosing, monitoring, and the evidence that separates rational use from dangerous misuse.
A medical student may first encounter it as a “respiratory fluoroquinolone” and memorize its mechanism. A clinician may reach for it when beta-lactams or macrolides are no longer reliable. A patient may search for Moxifloxacin Life-Saving Antibiotic or Dangerous Side Effects after receiving a prescription and wondering whether the benefits justify the risks. This article moves beyond a simple drug summary and provides a detailed, evidence-based exploration of moxifloxacin 400mg uses and side effects, covering moxifloxacin dosing, moxifloxacin adverse effects, moxifloxacin QT prolongation, moxifloxacin nerve damage, and much more.
If you are a medical student, pharmacist, nurse, physician, researcher, or an informed patient seeking clarity, this guide is designed for you. But here is the first clinical caution: this article does not replace professional diagnosis or treatment, and moxifloxacin should never be used for self-medication. The details that matter most will unfold section by section.
Before we go deeper, remember that clinical pharmacology is not about memorizing isolated facts. It is about understanding why a drug works, when it works, when it should be avoided, and what can go wrong. In the following sections, we answer those questions with evidence.
One more thing: if you are comparing fluoroquinolones and wondering about the older sibling, ciprofloxacin, you might be surprised by the hidden risks. For a suspenseful look at its uses and side effects, explore Details about Ciprofloxacin Uses and Side Effects. But keep your focus here first—the clinical stakes are high.
Key Facts Table: Moxifloxacin at a Glance
The following table summarizes the most clinically important facts about moxifloxacin. This is not a substitute for full prescribing information, but it provides a rapid reference for healthcare professionals and students.
| Parameter | Details |
|---|---|
| Generic Name | Moxifloxacin |
| Common Brand Names | Avelox (discontinued brand, generic available), Moxifloxacin HCl, Vigamox (ophthalmic), Moxeza (ophthalmic) |
| Drug Class | Fluoroquinolone antibiotic |
| Therapeutic Class | Antimicrobial / Antibacterial |
| Pharmacologic Class | DNA gyrase / Topoisomerase IV inhibitor |
| ATC Code | J01MA14 |
| Available Strengths | Tablet: 400 mg; Injection: 400 mg/250 mL; Ophthalmic solution: 0.5% |
| Dosage Forms | Oral tablet, intravenous (IV) solution, ophthalmic drops |
| Route(s) of Administration | Oral, IV, Ophthalmic |
| FDA Status | FDA-approved for specific bacterial infections in adults; not approved for children under 18 for systemic use |
| Primary Clinical Uses | Community-acquired pneumonia, complicated skin and skin structure infections, complicated intra-abdominal infections, acute bacterial sinusitis, acute bacterial exacerbation of chronic bronchitis, plague |
| Bioavailability | ~90% (oral) |
| Protein Binding | 30–50% |
| Volume of Distribution | 1.7–2.7 L/kg |
| Half-Life | 11–15 hours (prolonged in severe hepatic impairment) |
| Metabolism | Hepatic via glucuronide and sulfate conjugation; minimal CYP involvement |
| Major Route of Elimination | Fecal/biliary and renal (approximately 45% fecal, 20% renal unchanged) |
| Renal/Hepatic Considerations | No renal dose adjustment required; avoid in severe hepatic impairment |
| Major Contraindications | Known hypersensitivity to moxifloxacin or other fluoroquinolones |
| Important Adverse Effects | QT prolongation, tendinopathy, peripheral neuropathy, CNS effects, C. difficile-associated diarrhea, hepatotoxicity, dysglycemia, aortic aneurysm/dissection risk |
This table is a snapshot. Every parameter in it will be expanded in the dedicated sections below, but we will not repeat the full explanations unnecessarily.
What Is Moxifloxacin?
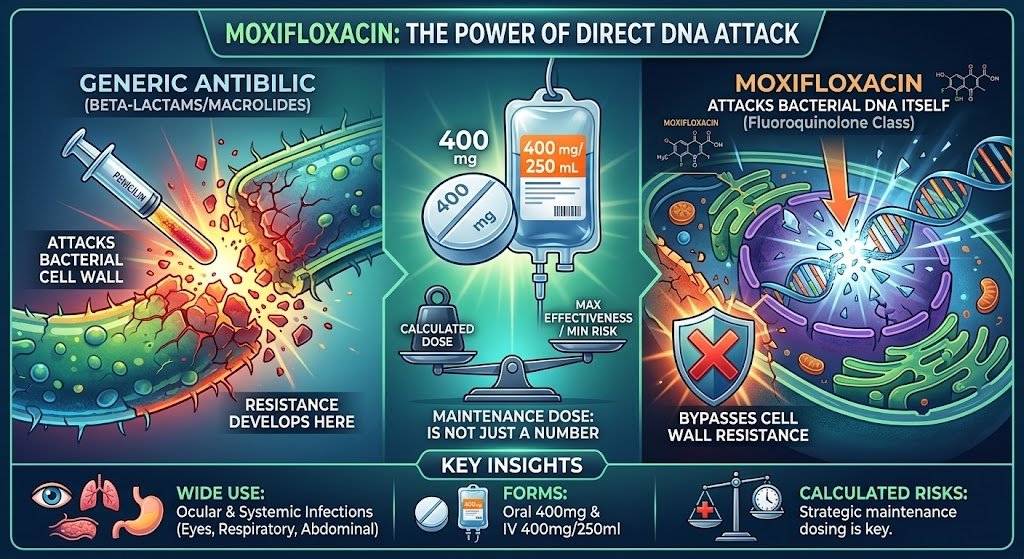
Moxifloxacin is a synthetic, broad-spectrum antibacterial agent belonging to the fluoroquinolone class. It is the 8-methoxy fluoroquinolone derivative of nalidixic acid. The drug is available as moxifloxacin hydrochloride for oral and intravenous use and as moxifloxacin ophthalmic solution for ocular infections. The systemic formulation is supplied as a 400 mg tablet and a 400 mg/250 mL ready-to-infuse IV solution. The ophthalmic formulation is a 0.5% solution.
As a fluoroquinolone antibiotic, moxifloxacin works by a mechanism fundamentally different from beta-lactams (like penicillins) or macrolides. While beta-lactams attack the bacterial cell wall, moxifloxacin attacks the bacterial DNA itself. This difference in target site is what allows moxifloxacin to be effective against bacteria that have developed resistance to other drug classes. The dose that maintains the effect is not just a number; it is a calculated risk. For a deeper understanding of how maintenance dosing works in pharmacology, visit Learn What is Half-Life of Medicines. This concept is vital for drugs like moxifloxacin where excretion is so tightly linked to organ function.
Moxifloxacin is considered a “respiratory fluoroquinolone” due to its enhanced activity against Streptococcus pneumoniae, including penicillin-resistant strains. This differentiates it from ciprofloxacin, which, while more potent against Pseudomonas aeruginosa, has weaker gram-positive coverage, making moxifloxacin a preferred choice for certain respiratory tract infections. Moxifloxacin also has clinically relevant anaerobic activity, which makes it useful in mixed infections.
Its availability in both oral and intravenous formulations is a major clinical advantage. Because its oral bioavailability is approximately 90%, a patient can be transitioned from IV to oral therapy without a change in dose, facilitating early hospital discharge and reducing healthcare costs. This pharmacologic profile explains why Moxifloxacin Life-Saving Antibiotic or Dangerous Side Effects differ from those of other fluoroquinolones.
The most commonly prescribed oral strength is moxifloxacin 400 mg, used for many adult indications. However, the dose must always be individualized based on infection severity, organism susceptibility, renal function, hepatic function, and patient-specific risk factors. Moxifloxacin for adults is straightforward in terms of dose, but the decision to use it is never routine. Moxifloxacin for children is not approved for systemic use, and pediatric dosing is not part of routine clinical practice.
Pharmacokinetics & Pharmacodynamics Key Table
Before we dive into individual pharmacokinetic sections, the following table provides a consolidated view of the clinically relevant pharmacokinetic and pharmacodynamic characteristics of moxifloxacin. The table is designed to be readable on mobile devices.
| Parameter | Clinically Relevant Details |
|---|---|
| Absorption | Rapid and well absorbed after oral administration. |
| Bioavailability | ~90%; oral dose approximates IV exposure. |
| Time to Peak Concentration | 1–3 hours post-dose (oral). |
| Protein Binding | Moderate (30–50%), allowing extensive tissue distribution. |
| Volume of Distribution | 1.7–2.7 L/kg, indicating excellent penetration into tissues and fluids. |
| Tissue Penetration | Excellent; achieves high concentrations in lung, sinus, skin, and peritoneal fluid. |
| Blood-Brain Barrier Penetration | Limited; not used for CNS infections. |
| Placental Transfer | Crosses the placenta; human data limited and require caution. |
| Half-Life | 11–15 hours in patients with normal hepatic function. |
| Metabolism | Hepatic via glucuronide and sulfate conjugation; minor CYP involvement. |
| Active Metabolites | None of clinical significance. |
| Enzyme Involvement | Minor CYP3A4/2C9; not a potent inhibitor or inducer. |
| Elimination | Fecal/biliary and renal; approximately 45% fecal, 20% renal unchanged. |
| Renal Clearance | Lower than glomerular filtration; tubular secretion occurs. |
| Fecal/Biliary Elimination | Significant; no dose reduction in mild to moderate hepatic impairment. |
| Pharmacodynamic Target | Inhibition of bacterial DNA gyrase and topoisomerase IV. |
| Mechanism | Bactericidal. |
| Concentration/Time-Dependent Activity | Concentration-dependent bactericidal activity with post-antibiotic effect. |
| PK/PD Index | AUC/MIC ratio is the best predictor of efficacy. |
This table is a quick reference. The following sections explain the most important details without unnecessary repetition.
Half-Life of Moxifloxacin
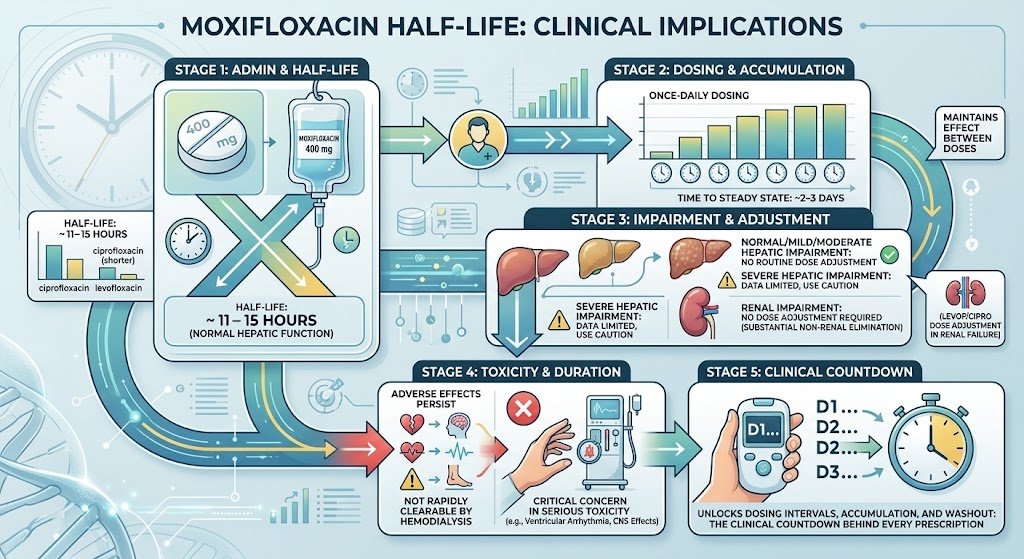
The half-life of moxifloxacin in a patient with normal hepatic function is approximately 11 to 15 hours. This relatively long half-life permits once-daily dosing of 400 mg for systemic infections. The half-life is longer than that of ciprofloxacin and comparable to levofloxacin, though moxifloxacin’s half-life can be slightly more variable in older adults and patients with hepatic impairment. The drug’s half-life matters clinically because it determines the time to steady state—approximately 2 to 3 days—and influences the duration of antimicrobial effect after the last dose.
In patients with mild to moderate hepatic impairment, the half-life may be modestly prolonged, but the change is generally not considered clinically significant enough to require routine dose adjustment. In severe hepatic impairment, data are limited. Renal impairment does not significantly prolong moxifloxacin half-life because the drug undergoes substantial non-renal elimination. This is a key contrast with levofloxacin and ciprofloxacin, both of which require dose adjustment in reduced renal function.
Why does half-life matter beyond dosing frequency? Because a drug with an 11–15 hour half-life maintains therapeutic concentrations for a meaningful period after oral or IV administration. However, it also means that if a serious adverse effect occurs—such as QT prolongation, CNS toxicity, or tendinopathy—the drug cannot be rapidly cleared by hemodialysis. The half-life is not modifiable by common dialysis techniques. This becomes critically important when a patient on moxifloxacin develops severe neuropsychiatric symptoms or ventricular arrhythmia. For a deeper understanding of how half-life governs dosing intervals, accumulation, and drug washout, this complete guide reveals the clinical countdown behind every prescription: Half-Life of Medicines: Complete Guide.
Another subtle clinical point: the long half-life allows once-daily dosing but also delays complete washout. If a clinician needs to switch to another interacting drug, the moxifloxacin effect may persist for days after discontinuation. This is why drug interaction management requires awareness of the half-life, not just the dose. Patients should be counseled that adverse effects such as tendon pain or nerve tingling may begin during treatment or even weeks after the last dose. The half-life alone does not fully explain delayed fluoroquinolone toxicity, but it contributes to the lingering pharmacologic presence.
Metabolism of Moxifloxacin
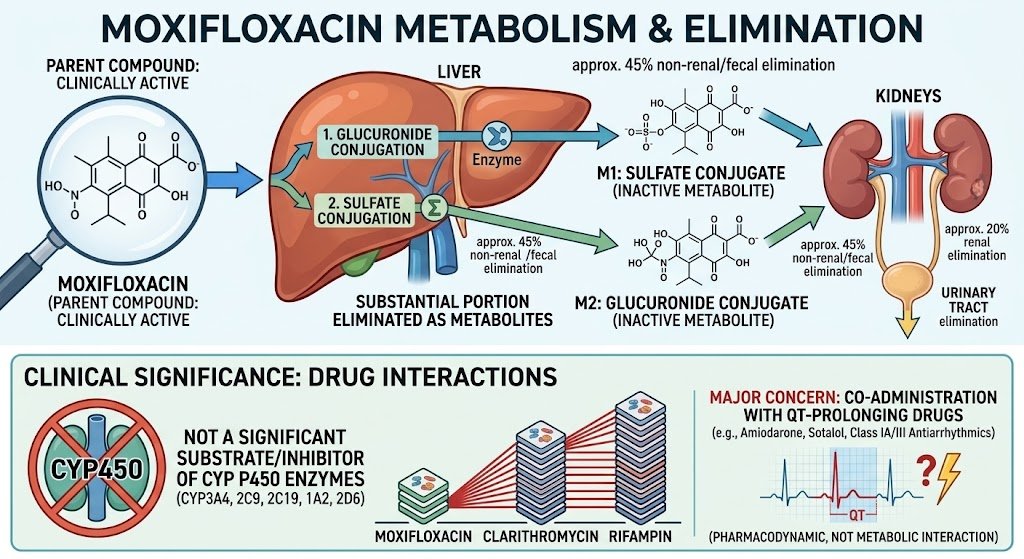
In contrast to many other drugs, moxifloxacin undergoes limited hepatic metabolism. The drug is primarily metabolized through glucuronide and sulfate conjugation to form two major metabolites: M1, a sulfate conjugate, and M2, a glucuronide conjugate. These metabolites account for a substantial portion of the drug’s elimination, but they are not considered clinically active antimicrobials. The parent compound is responsible for the therapeutic effect.
Moxifloxacin is not a significant substrate for cytochrome P450 enzymes, and it does not potently inhibit CYP3A4, CYP2C9, CYP2C19, CYP1A2, or CYP2D6. This is clinically important because moxifloxacin has fewer CYP-mediated drug interactions than drugs like clarithromycin or rifampin. However, co-administration with drugs that prolong the QT interval is still a major concern, but that interaction is pharmacodynamic, not metabolic.
The hepatic conjugation pathways are generally preserved in mild to moderate liver disease. However, because the liver is a major route of elimination, severe hepatic impairment may reduce clearance and increase exposure. The FDA labeling does not recommend a specific dose adjustment for mild to moderate hepatic impairment, but the drug should be used with caution in severe hepatic disease. Monitoring for adverse effects may be appropriate in this population.
The renal route handles approximately 20% of an administered dose as unchanged drug, with additional amounts as metabolites. This explains why renal impairment does not require dose adjustment for moxifloxacin. But it also means that moxifloxacin is not ideal for urinary tract infections because active drug concentrations in urine may be lower than those achieved by ciprofloxacin or levofloxacin. The metabolic profile, therefore, shapes both safety and efficacy.
For clinicians, the metabolism section answers a common question: “Can I use moxifloxacin in a patient on multiple CYP-metabolized medications?” The answer is generally yes from a CYP perspective, but the patient’s QT risk, electrolyte status, and central nervous system history must still be reviewed. Metabolism is one piece of the interaction puzzle. Moxifloxacin’s minimal CYP involvement does not make it a universally safe drug.
Bioavailability & Protein Binding of Moxifloxacin
One of the most useful features of moxifloxacin is its oral bioavailability of approximately 90%. This means that when a patient swallows a 400 mg tablet, the body absorbs almost the entire dose, achieving blood levels nearly identical to those achieved by a 400 mg intravenous infusion. This is the foundation of “IV-to-PO switch” therapy. A patient stabilized on IV moxifloxacin can be switched to an oral tablet at the same dose with confidence, freeing them from IV lines and enabling earlier discharge.
Food does not significantly reduce the extent of moxifloxacin absorption, although it may slightly delay the time to peak concentration. However, divalent and trivalent cations—such as calcium, magnesium, iron, zinc, and aluminum—can chelate moxifloxacin in the gut and substantially reduce its absorption. This is the foundation of the moxifloxacin with dairy products warning. Dairy foods are rich in calcium. If moxifloxacin is taken simultaneously with milk, yogurt, or cheese, the drug may bind to calcium and form poorly absorbed complexes. The result is lower serum concentrations and potential treatment failure.
The clinical instruction is to separate moxifloxacin from dairy products, antacids, iron supplements, zinc-containing multivitamins, sucralfate, and didanosine buffered tablets by at least 4 hours before or 8 hours after the moxifloxacin dose. Moxifloxacin with food is generally acceptable, but the specific components of the meal matter. A high-calcium meal is not the same as a standard meal. This distinction is not always communicated clearly to patients, and it contributes to real-world treatment failures.
Moxifloxacin is approximately 30 to 50% bound to plasma proteins, primarily albumin. This is relatively low compared with many other drugs. The clinical significance of protein binding is that only unbound drug is pharmacologically active and capable of tissue diffusion. Because moxifloxacin has moderate protein binding and a large volume of distribution, it achieves high concentrations in tissues such as lung epithelial lining fluid, alveolar macrophages, sinus mucosa, and skin blister fluid. For respiratory infections, this tissue penetration is a therapeutic advantage. For a broader context on why this concept matters for nearly every medication, the principles governing this behavior are discussed in our comprehensive guide on Learn Details of Plasma Protein Binding.
In hypoalbuminemic patients—such as those with severe sepsis, burns, or malnutrition—the unbound fraction of moxifloxacin may increase. This could theoretically enhance antimicrobial activity but also increase the risk of concentration-dependent toxicities. However, because moxifloxacin is not highly protein-bound, the clinical impact of hypoalbuminemia is less pronounced than with highly bound drugs. Still, in critically ill patients, changes in volume of distribution and protein binding are reasons why fixed doses may not always behave identically across all populations.
FDA-Approved Uses: The Six Critical Indications
When we discuss moxifloxacin uses and side effects, we must first ground our conversation in the diseases it is officially approved to treat. The FDA has carefully delineated these indications because the drug’s power is balanced by its risk. These are not first-line uses; they are strategic ones.
1. Community-Acquired Pneumonia (CAP) 
Moxifloxacin is FDA-approved for the treatment of community-acquired pneumonia caused by susceptible strains of Streptococcus pneumoniae (including multidrug-resistant strains), Haemophilus influenzae, Moraxella catarrhalis, Staphylococcus aureus, Klebsiella pneumoniae, Mycoplasma pneumoniae, Chlamydophila pneumoniae, and Legionella pneumophila. Its role here is significant when first-line options are not viable, the patient has significant comorbidities, or resistant pneumococci are suspected. The suspense here is high; severe pneumonia can be rapidly fatal, and moxifloxacin’s rapid, concentration-dependent killing and excellent lung penetration can be life-saving.
2. Acute Bacterial Sinusitis (ABS) 
While antibiotics are often misused for viral sinusitis, moxifloxacin is approved for acute bacterial sinusitis caused by susceptible organisms. However, due to its serious side effect profile, major guidelines typically reserve moxifloxacin for patients who have failed first-line therapy (like amoxicillin-clavulanate) or who have a history of severe beta-lactam allergy. In this context, it is a “rescue” medication.
3. Acute Bacterial Exacerbation of Chronic Bronchitis (ABECB) 
This is an infection that occurs in patients with chronic obstructive pulmonary disease (COPD). Moxifloxacin is approved for treating ABECB caused by Staphylococcus aureus, S. pneumoniae, H. influenzae, Haemophilus parainfluenzae, or Moraxella catarrhalis. Again, stewardship principles dictate it should not be used when narrower-spectrum agents are effective.
4. Complicated Skin and Skin Structure Infections (cSSSI) 
Moxifloxacin is approved for complicated skin and skin structure infections, including diabetic foot infections, caused by susceptible organisms such as methicillin-susceptible Staphylococcus aureus, Escherichia coli, Klebsiella pneumoniae, and Enterobacter cloacae. The drug’s anaerobic activity also makes it useful in mixed aerobic-anaerobic soft tissue infections. It is not active against methicillin-resistant Staphylococcus aureus, and it should not be used as empirical monotherapy when MRSA is suspected.
5. Complicated Intra-Abdominal Infections (cIAI)
Moxifloxacin is approved for complicated intra-abdominal infections, including polymicrobial infections such as abscesses, caused by susceptible organisms. Its anaerobic coverage includes Bacteroides fragilis and other anaerobes. However, increasing Bacteroides resistance has led some guidelines to prefer other regimens. Moxifloxacin may be used in combination with metronidazole if local resistance rates are concerning.
6. Plague

Moxifloxacin is FDA-approved for the treatment of plague, including pneumonic and septicemic plague, caused by Yersinia pestis. This approval was based on animal efficacy studies because human trials for plague are not feasible. It is also approved for post-exposure prophylaxis of plague. This is one of the clearest examples of moxifloxacin life saving antibiotic. In a bioterrorism or endemic plague scenario, the drug can be rapidly administered orally or intravenously with high tissue penetration and a convenient once-daily regimen.
Off-Label and Guideline-Supported Uses
Moxifloxacin is sometimes used off-label in specific mycobacterial infections, particularly as part of multidrug regimens for tuberculosis and nontuberculous mycobacteria. The World Health Organization and other guidelines classify moxifloxacin as a second-line or group A/B agent in drug-resistant tuberculosis. It is also used off-label for nocardiosis, certain ocular infections, and selected cases of osteomyelitis. These uses are not FDA-approved and require specialist input. The drug should never be labeled as “approved” for these conditions. The line between approval and evidence-based practice is clinically meaningful.
Spectrum of Activity: The Broad-Spectrum Warrior
Beyond its FDA-approved uses, understanding moxifloxacin’s spectrum of activity is essential for a clinician deciding when to deploy it. Its clinical success is directly tied to which bacteria it can kill.
Gram-Positive Activity
Moxifloxacin is highly active against gram-positive organisms, making it a potent respiratory fluoroquinolone. This includes Streptococcus pneumoniae (a key strength, including activity against many penicillin-resistant strains and macrolide-resistant strains) and Staphylococcus aureus (active against MSSA, but not against community-acquired methicillin-resistant Staphylococcus aureus (CA-MRSA)). This is a critical limitation. Prescribing moxifloxacin for a suspected MRSA skin infection would be a clinical failure.
Gram-Negative Activity
Its gram-negative coverage is broad, though generally less potent against Pseudomonas than ciprofloxacin. It is active against many Enterobacteriaceae including E. coli, Klebsiella, Proteus, and Enterobacter species. However, fluoroquinolone resistance among these organisms is a growing global crisis, often linked to overuse. It has excellent activity against Haemophilus influenzae and Moraxella catarrhalis. For Pseudomonas aeruginosa, moxifloxacin is not a reliable empirical agent. If you are comparing fluoroquinolones, our piece on Facts About Ciprofloxacin Uses and Side Effects offers a useful contrast, as ciprofloxacin is the fluoroquinolone of choice for serious P. aeruginosa infections when a quinolone is needed.
Anaerobic Activity
Moxifloxacin has enhanced anaerobic activity compared with ciprofloxacin and levofloxacin. It is active against Bacteroides fragilis, Peptostreptococcus species, and many other anaerobes. This supports its use in complicated intra-abdominal infections and mixed skin infections. However, rising Bacteroides resistance has been reported in some regions, and susceptibility testing is recommended when anaerobic coverage is critical.
Atypical Organisms
This is a major therapeutic advantage. Moxifloxacin is highly effective against “atypical” intracellular bacteria that are inherently resistant to beta-lactams: Mycoplasma pneumoniae, Chlamydophila pneumoniae, and Legionella pneumophila. This “triple coverage” (gram-positive, gram-negative, and atypical) in one oral pill is what makes moxifloxacin so valuable for treating community-acquired pneumonia when the pathogen is unknown.
Important Intrinsic Resistance
Like all fluoroquinolones, moxifloxacin has poor activity against Enterococcus faecium, most MRSA, Pseudomonas aeruginosa, Acinetobacter baumannii, and many extended-spectrum beta-lactamase-producing Enterobacterales. Acquired resistance typically occurs via mutations in the genes encoding DNA gyrase or topoisomerase IV, or via efflux pumps that remove the drug from the bacterial cell. This is why susceptibility testing is non-negotiable for serious infections.
Mechanism of Action: Moxifloxacin
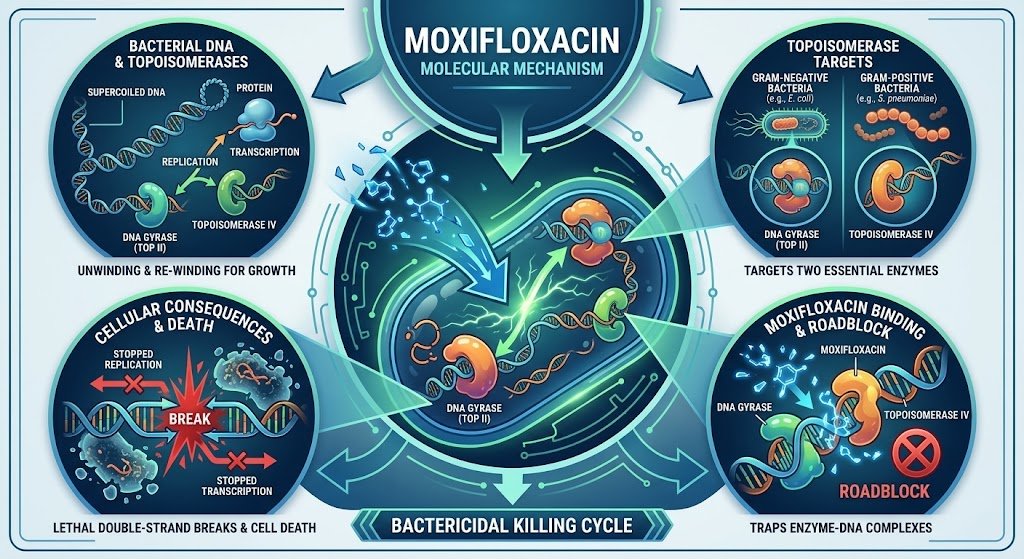
The molecular mechanism of moxifloxacin is elegant and brutal. It is a bactericidal agent that kills bacteria by corrupting their most fundamental blueprint: DNA. Bacterial DNA is a long, supercoiled structure that must be unwound and re-wound continuously for the cell to replicate and synthesize proteins. This process is managed by essential enzymes called topoisomerases. Moxifloxacin targets two of these enzymes:
DNA gyrase (Topoisomerase II): This enzyme is primarily responsible for introducing negative supercoils into DNA, allowing it to unwind for replication. It is the main target in gram-negative bacteria.
Topoisomerase IV: This enzyme is responsible for “decatenating” or unlinking the two newly replicated DNA molecules. It is the primary target in many gram-positive bacteria like S. pneumoniae and S. aureus.
Moxifloxacin binds to these enzyme-DNA complexes, trapping them in a state where they are stuck. This creates a roadblock on the DNA strand. The trapped complex prevents DNA replication and RNA transcription, leading to irreversible DNA damage and the generation of lethal double-strand breaks. The cell dies—a process known as bactericidal killing.
This unique mechanism explains why moxifloxacin works when other antibiotics fail. Bacteria that have become resistant to beta-lactams (by altering their cell wall proteins) or to macrolides (by modifying their ribosomes) have not yet developed resistance to a drug that attacks their DNA. However, when bacteria do develop resistance to moxifloxacin, it is often via target-site mutations that change the shape of the gyrase or topoisomerase, preventing the drug from binding. The same mechanism that kills bacteria may also damage human mitochondrial DNA. This is one proposed explanation for fluoroquinolone toxicity, including tendinopathy, neuropathy, and other delayed adverse effects.
Pharmacodynamics of Moxifloxacin
The pharmacodynamic principle underlying moxifloxacin is simple: “higher concentration equals faster and more complete killing.” This is known as concentration-dependent bactericidal activity. Unlike beta-lactams, which require drug levels to stay above the MIC for a prolonged period (time-dependent killing), moxifloxacin’s efficacy is optimized when the peak drug concentration is high.
The best predictor of clinical success is the ratio of the AUC (Area Under the Curve) to MIC. For moxifloxacin, an AUC/MIC ratio of >30–50 is generally required for gram-positive infections, and >125 for severe gram-negative infections. Achieving these high ratios is the goal of dosing.
This concentration-dependent activity also leads to a post-antibiotic effect (PAE). This means that even after drug levels fall below the MIC, bacterial growth remains suppressed for a period. This supports the once-daily dosing regimen. The goal is to deliver a high enough dose to maximize the AUC/MIC ratio and achieve rapid bacterial eradication, while also minimizing the risk of resistance emergence. Dosing too low is a recipe for clinical failure and the selection of resistant mutants.
The therapeutic window is limited not only by efficacy but also by safety. Moxifloxacin prolongs the QT interval in a concentration-dependent manner. Higher plasma concentrations are associated with greater QT prolongation. This is one reason the dose is fixed at 400 mg daily and not escalated. It also means that factors increasing moxifloxacin exposure—such as severe hepatic impairment, drug interactions, or advanced age—may increase the risk of cardiac arrhythmia risk. The drug’s pharmacodynamic profile is a balancing act between achieving sufficient AUC/MIC for bacterial killing and avoiding excessive exposure that could trigger toxicity.
Contraindications: The Absolute No-Fly Zones
The power of moxifloxacin is matched by its potential for harm. There are situations where the risk is categorically unacceptable. These are the absolute contraindications.
Hypersensitivity
Moxifloxacin is contraindicated in patients with a known history of a severe hypersensitivity reaction (anaphylaxis, Stevens-Johnson Syndrome, toxic epidermal necrolysis) to moxifloxacin or any other member of the fluoroquinolone class, such as ciprofloxacin, levofloxacin, or ofloxacin. A serious allergic reaction is an absolute bar to re-exposure.
Concomitant QT-Prolonging Drugs
Although not always listed as a strict contraindication, moxifloxacin should be avoided in patients with known QT interval prolongation, uncorrected hypokalemia, clinically significant bradycardia, or concurrent use of Class IA or Class III antiarrhythmic agents. The FDA labeling includes strong warnings about QT prolongation. Some international labels list these conditions as contraindications. The risk of torsades de pointes is real and can be fatal.
History of Fluoroquinolone-Associated Tendinopathy
Moxifloxacin is contraindicated in patients with a history of fluoroquinolone-associated tendon disorders, such as tendinitis or tendon rupture. A prior episode of fluoroquinolone-induced peripheral neuropathy is also a strong reason to avoid re-challenge, although labeling may not always list it as an absolute contraindication. The principle is simple: a serious, disabling adverse effect from a fluoroquinolone should generally lead to avoidance of the entire class unless no alternative exists.
Children Under 18 Years
The systemic formulation is not approved for use in children under 18 years of age. This is due to fluoroquinolone-associated cartilage damage observed in juvenile animal studies. The ophthalmic formulation has a different risk profile and may be used in younger patients for bacterial conjunctivitis, but systemic use in pediatrics is reserved for exceptional situations where the benefit clearly outweighs the risk, such as multidrug-resistant tuberculosis or plague.
Severe Hepatic Impairment
Moxifloxacin is not recommended in patients with severe hepatic impairment because data are limited and the risk of toxicity may be increased. This is a precaution rather than an absolute contraindication, but it is clinically important.
Warnings & Precautions: Navigating the Minefield
Here lies the heart of the clinical debate about moxifloxacin. Its toxicity profile is significant enough that the FDA has issued multiple Black Box Warnings, the strongest available. These warnings are not theoretical; they represent real, potentially permanent disabilities. The decision to prescribe this drug is a calculated risk.
QT Prolongation and Cardiac Arrhythmia Risk
Moxifloxacin prolongs the QTc interval by approximately 6 to 14 milliseconds at standard doses. In susceptible individuals, this can progress to torsades de pointes and ventricular fibrillation. The risk is higher in patients with pre-existing QT prolongation, electrolyte abnormalities—especially hypokalemia and hypomagnesemia—concomitant QT-prolonging drugs, bradycardia, heart failure, or advanced age. Monitoring includes baseline and follow-up ECG in high-risk patients. This is a core component of moxifloxacin dangerous side effects.
Tendinopathy and Tendon Rupture
Fluoroquinolones, including moxifloxacin, increase the risk of tendinitis and tendon rupture. The Achilles tendon is most commonly affected, but the shoulder, hand, and other tendons can also be involved. Risk is higher in patients over 60, those on corticosteroids, and kidney, heart, or lung transplant recipients. Tendon rupture can occur during treatment or months after discontinuation. Patients should stop moxifloxacin at the first sign of tendon pain and seek medical evaluation.
Peripheral Neuropathy
Moxifloxacin can cause peripheral neuropathy that may be rapid in onset and permanent. Symptoms include pain, burning, tingling, numbness, weakness, and altered sensation. The FDA has warned that nerve damage may occur within days of starting fluoroquinolone treatment. The question “moxifloxacin nerve damage permanent” is frequently searched because the damage can be irreversible. Patients should discontinue the drug immediately if neuropathic symptoms appear. This is not a side effect to watch and wait through.
CNS Effects
Fluoroquinolones can cause dizziness, confusion, seizures, increased intracranial pressure, hallucinations, and psychiatric disturbances. Patients with epilepsy, cerebral atherosclerosis, or other CNS disorders may be at higher risk. Moxifloxacin should be used with caution in these populations. Elderly patients may develop delirium or psychosis. The CNS effects are generally reversible after discontinuation, but they can be severe enough to require hospitalization.
Clostridioides difficile-Associated Diarrhea
Moxifloxacin use can lead to C. difficile infection, which may range from mild diarrhea to fulminant colitis. This risk is common to nearly all antibiotics but is especially relevant for fluoroquinolones. C. difficile infection can occur weeks after antibiotic discontinuation. Any diarrhea during or after moxifloxacin therapy should be evaluated for C. difficile before using antimotility agents.
Hepatotoxicity
Moxifloxacin can cause severe liver injury, including hepatitis, jaundice, and acute hepatic necrosis. Fatal cases have been reported. Patients should be counseled to report dark urine, jaundice, abdominal pain, or unusual fatigue. Liver function tests may be monitored in patients with pre-existing liver disease or those who develop symptoms of hepatotoxicity.
Dysglycemia
Fluoroquinolones have been associated with both hypoglycemia and hyperglycemia. Moxifloxacin may cause blood glucose disturbances, particularly in patients with diabetes. Severe hypoglycemia can lead to coma. Blood glucose monitoring should be considered in diabetic patients during moxifloxacin therapy.
Aortic Aneurysm and Dissection
Epidemiological studies have suggested an association between fluoroquinolone use and aortic aneurysm or dissection, particularly in older adults and patients with hypertension, Marfan syndrome, or vascular disease. Moxifloxacin should be avoided in patients with known aortic aneurysm or significant risk factors unless no alternative exists.
Hypersensitivity Reactions
Serious and sometimes fatal hypersensitivity reactions can occur with moxifloxacin, including anaphylaxis, Stevens-Johnson syndrome, and toxic epidermal necrolysis. These reactions may occur with the first dose or after multiple doses. Patients with a history of quinolone hypersensitivity should never receive moxifloxacin.
Side Effects of Moxifloxacin
Understanding the moxifloxacin side effects profile requires separating common, often self-limited reactions from less common but serious adverse events. The following sections describe both categories.
Common Side Effects
Common side effects of moxifloxacin are generally mild to moderate and may include nausea, diarrhea, vomiting, abdominal discomfort, headache, dizziness, and insomnia. These gastrointestinal and CNS effects are the most frequently reported adverse reactions in clinical trials.
Nausea and diarrhea occur because moxifloxacin alters the normal gut microbiota. Taking moxifloxacin with food may reduce nausea but can delay absorption. Patients should be advised to stay hydrated, especially if diarrhea is significant. Headache and dizziness are usually transient but should be reported if they worsen or interfere with daily activities.
Insomnia and restlessness are also reported. Because moxifloxacin can cause CNS stimulation, some patients may experience difficulty sleeping, particularly if the evening dose is taken too close to bedtime. Taking the last dose earlier in the evening may help, but this should be discussed with a healthcare provider.
Less Common Side Effects
Less common side effects include photosensitivity reactions, visual disturbances, tinnitus, dysgeusia, and mild transaminase elevations. These reactions are generally reversible upon discontinuation. Photosensitivity is particularly important because it can occur with even brief sun exposure. Patients should be counseled to use sun protection.
Candidiasis, or oral or vaginal yeast infection, can occur because moxifloxacin suppresses normal bacterial flora, allowing fungal overgrowth. This is a common antibiotic-associated complication and can be treated with antifungal therapy if needed. While general wellness and beauty tips can support overall health, they are never a substitute for clinical monitoring. For lifestyle-oriented health information that complements medical care, ssthem.net for Health and Beauty Tips offers accessible guidance.
Adverse Effects of Moxifloxacin
The adverse effects of moxifloxacin are more serious than the common side effects described above. These reactions may be rare, but they can be severe, disabling, or life-threatening. Healthcare professionals must recognize them early, and patients must know when to seek emergency care.
Cardiac Arrhythmia Risk
Moxifloxacin can cause QT prolongation, which may progress to torsades de pointes, a polymorphic ventricular tachycardia that can degenerate into ventricular fibrillation and sudden cardiac death. Patients with pre-existing cardiac disease, electrolyte abnormalities, or concurrent QT-prolonging medications are at highest risk. Symptoms of arrhythmia include palpitations, syncope, seizures, or sudden death. This is one of the most dangerous adverse effects of moxifloxacin.
Fluoroquinolone Toxicity Syndrome
The term fluoroquinolone toxicity describes a constellation of potentially irreversible adverse effects, including tendinopathy, peripheral neuropathy, autonomic dysfunction, cognitive impairment, and musculoskeletal pain. This syndrome is not universally recognized in all medical circles, but the FDA has acknowledged that serious, disabling, and potentially permanent adverse reactions can occur. Moxifloxacin nerve damage permanent is a real concern. Patients with prior fluoroquinolone toxicity should avoid all fluoroquinolones.
Severe Dermatologic Reactions
Stevens-Johnson syndrome, toxic epidermal necrolysis, and drug reaction with eosinophilia and systemic symptoms can occur with moxifloxacin. These reactions are rare but life-threatening. Early signs include fever, mucosal ulcers, skin pain, and a spreading rash. Immediate discontinuation and emergency care are required.
Hepatotoxicity
Severe liver injury, including acute liver failure, has been reported. The exact incidence is low, but the outcome can be fatal. Jaundice, dark urine, right upper quadrant pain, and coagulopathy are warning signs. Moxifloxacin should be stopped immediately in patients with suspected drug-induced liver injury.
Hematologic Effects
Agranulocytosis, aplastic anemia, and hemolytic anemia have been reported with fluoroquinolones, although they are rare with moxifloxacin. Blood dyscrasias may present as fever, sore throat, pallor, or bleeding. Complete blood count monitoring is not routinely required, but clinicians should remain alert to symptoms.
Ocular Effects
Retinal detachment has been reported in some fluoroquinolone studies, although the absolute risk is low. Patients with pre-existing retinal disease may be at higher risk. New visual symptoms during moxifloxacin therapy should prompt urgent ophthalmologic evaluation.
Drug Interactions of Moxifloxacin
Moxifloxacin drug interactions are clinically significant and must be reviewed before prescribing or dispensing. The table below summarizes the most important interactions. This is not an exhaustive list, but it highlights interactions with strong evidence and clinical relevance.
| Interacting Medicine/Class | Potential Interaction | Clinical Significance | Management Consideration |
|---|---|---|---|
| Antacids containing aluminum/magnesium | Reduced moxifloxacin absorption | Major | Separate administration by 4 hours before or 8 hours after |
| Calcium, iron, zinc supplements | Chelation and reduced absorption | Major | Separate administration |
| Sucralfate | Reduced moxifloxacin absorption | Major | Separate dosing or avoid |
| Didanosine buffered tablets | Reduced moxifloxacin absorption | Major | Administer moxifloxacin 2 hours before or 6 hours after |
| Class IA antiarrhythmics | Additive QT prolongation | Major | Avoid concurrent use |
| Class III antiarrhythmics | Additive QT prolongation | Major | Avoid concurrent use |
| Macrolides (erythromycin, clarithromycin) | Additive QT prolongation | Major | Avoid or monitor ECG |
| Antipsychotics (haloperidol, ziprasidone) | Additive QT prolongation | Moderate to major | Monitor ECG and electrolytes |
| Corticosteroids | Increased risk of tendon rupture | Major | Avoid combination if possible; counsel patient |
| Warfarin | Enhanced anticoagulant effect | Moderate | Monitor INR closely |
| Oral hypoglycemics/insulin | Blood glucose disturbances | Moderate | Monitor blood glucose in diabetics |
| NSAIDs | Possible increased CNS stimulation | Moderate | Use caution in patients with seizure history |
Moxifloxacin with Dairy Products
The question of moxifloxacin with dairy products is critical. Calcium in milk, yogurt, and cheese binds moxifloxacin in the gastrointestinal tract, forming insoluble complexes that reduce drug absorption. This can lower serum moxifloxacin concentrations below the level needed to treat the infection. Patients should not take moxifloxacin with milk alone or with a dairy-heavy meal. Instead, moxifloxacin should be taken either two hours before or at least four to six hours after dairy products. The same applies to calcium-fortified juices and supplements.
Moxifloxacin with Food
The timing question—moxifloxacin with food—is common. Moxifloxacin can be taken with or without food. Taking it with food may reduce nausea. However, food, especially dairy or calcium-containing foods, can delay absorption. The most important instruction is to avoid taking moxifloxacin with milk, yogurt, or calcium-fortified products. If a patient takes moxifloxacin with a meal, the meal should not be dairy-heavy and should not contain antacids or mineral supplements.
Dosage Details of Moxifloxacin
Moxifloxacin dosage depends on the infection type, severity, hepatic function, patient age, and local resistance patterns. The following are general adult doses for selected indications. These doses are based on prescribing information and should not replace clinical judgment or current guidelines.
Community-Acquired Pneumonia
For community-acquired pneumonia, the typical regimen is moxifloxacin 400 mg IV or orally once daily for 7 to 14 days. The duration depends on clinical response and severity.
Skin and Skin Structure Infections
For complicated skin and skin structure infections, moxifloxacin 400 mg IV or orally once daily for 7 to 21 days may be used, depending on infection site and response.
Complicated Intra-Abdominal Infections
For complicated intra-abdominal infections, moxifloxacin 400 mg IV once daily for 5 to 14 days is typical. Initiate IV therapy and consider oral step-down when the patient is stable and tolerating oral intake.
Acute Bacterial Sinusitis
For acute bacterial sinusitis, moxifloxacin 400 mg once daily for 7 to 10 days is typical, reserved for patients without alternative options.
Acute Bacterial Exacerbation of Chronic Bronchitis
For ABECB, moxifloxacin 400 mg orally once daily for 5 days is typical.
Plague
For plague, moxifloxacin 400 mg IV or orally once daily for 10 to 14 days is recommended.
Renal Impairment
No dose adjustment is required in renal impairment, including patients on hemodialysis or peritoneal dialysis. This is a significant difference from levofloxacin and ciprofloxacin, both of which require renal dose adjustment.
Hepatic Impairment
In mild to moderate hepatic impairment, no dose adjustment is required. In severe hepatic impairment, the drug should be avoided because the liver is a major route of elimination and data are insufficient to guide safe dosing.
Pediatric Dosing
Systemic moxifloxacin is not approved for children under 18 years of age. Pediatric dosing is not part of routine clinical practice, except for exceptional life-threatening infections under specialist care.
Dosage Table
The table below provides a concise summary of typical adult dosing for common indications. Doses may vary based on hepatic function, severity, and susceptibility data.
| Patient/Condition | Recommended Dose | Frequency | Duration | Important Considerations |
|---|---|---|---|---|
| Community-acquired pneumonia | 400 mg IV/oral | Once daily | 7–14 days | Use in severe or resistant cases |
| Acute bacterial sinusitis | 400 mg oral | Once daily | 7–10 days | Reserve for no alternative options |
| ABECB | 400 mg oral | Once daily | 5 days | Use only when alternatives inadequate |
| Complicated skin and skin structure infection | 400 mg IV/oral | Once daily | 7–21 days | Not for MRSA |
| Complicated intra-abdominal infection | 400 mg IV | Once daily | 5–14 days | Initiate IV; oral step-down when appropriate |
| Plague | 400 mg IV/oral | Once daily | 10–14 days | Life-threatening infection |
| Renal impairment | 400 mg | Once daily | Standard duration | No dose adjustment required |
| Severe hepatic impairment | Not recommended | — | — | Limited data; increased exposure possible |
Administration Table
Practical administration instructions are essential for patient education and nursing practice. The table below summarizes key administration factors.
| Administration Factor | Guidance |
|---|---|
| Route | Oral, intravenous, ophthalmic |
| With Food/Without Food | May be taken with or without food; avoid dairy or calcium-fortified products within 4 hours before or 8 hours after |
| Timing | Once daily at the same time each day |
| Tablet/Capsule Instructions | Swallow whole with water; do not crush or chew |
| IV Administration | Infuse over 60 minutes; do not administer as bolus |
| Missed Dose | Take as soon as remembered unless close to next dose; do not double dose |
| Storage | Store at room temperature 15–30°C; protect from moisture |
| Special Instructions | Avoid dairy and mineral supplements near dose; report tendon pain or neuropathy immediately |
When a patient asks about moxifloxacin missed dose, the answer should be clear: if a dose is missed, take it as soon as possible unless it is nearly time for the next scheduled dose. In that case, skip the missed dose and continue the regular schedule. Never double the dose to make up for a missed one, because that increases the risk of adverse effects without improving efficacy.
Pharmacokinetics of Moxifloxacin
This consolidated pharmacokinetics section provides a professional overview without repeating the detailed half-life, metabolism, and bioavailability discussions already presented.
Absorption
Moxifloxacin is rapidly absorbed after oral administration. Peak serum concentrations occur approximately 1 to 3 hours after a dose. Food delays absorption but does not significantly reduce overall bioavailability. Dairy products and mineral-containing supplements reduce absorption through chelation.
Distribution
Moxifloxacin has a large volume of distribution, reflecting extensive tissue penetration. It distributes widely into the lungs, sinuses, skin, peritoneal fluid, and macrophages. Cerebrospinal fluid concentrations are limited, and the drug is not used for central nervous system infections. The drug crosses the placenta and is excreted in breast milk.
Bioavailability and Protein Binding
As discussed in the Bioavailability & Protein Binding section, oral bioavailability is approximately 90%, and protein binding is moderate at 30–50%. This supports the use of oral therapy for many serious infections.
Metabolism and Half-Life
As discussed in the Metabolism and Half-Life sections, moxifloxacin undergoes hepatic conjugation with minimal CYP involvement and has a half-life of approximately 11 to 15 hours in adults with normal hepatic function.
Elimination
Fecal/biliary and renal elimination are the major routes of clearance. Approximately 45% of an administered dose appears in feces, and about 20% as unchanged drug in urine. Biliary and fecal elimination account for a significant fraction. Dose adjustment is not required in renal impairment but is not recommended in severe hepatic impairment.
Special Populations
Moxifloxacin During Pregnancy
Moxifloxacin crosses the placenta. Animal studies have shown an increased risk of fetal skeletal malformations and reduced fetal body weight at high doses. Human data are limited, and moxifloxacin is generally avoided during pregnancy unless no safer alternative is available and the clinical benefit clearly outweighs the risk. Moxifloxacin during pregnancy should involve a specialist consultation.
Moxifloxacin During Breastfeeding
Moxifloxacin is excreted into human breast milk in small amounts. The effects on the nursing infant are not well studied. Because fluoroquinolones can cause arthropathy in immature animals, caution is advised. The recommendation is usually to avoid moxifloxacin during breastfeeding or to discontinue breastfeeding temporarily during treatment. The decision should involve the mother’s clinical need and the infant’s risk.
Pediatrics
Systemic moxifloxacin is not approved for children under 18 years of age. Juvenile animal studies showed cartilage damage and arthropathy. However, in selected life-threatening infections such as multidrug-resistant tuberculosis, moxifloxacin has been used off-label in children under specialist care. The risk-benefit balance is different in these cases, but routine use is not acceptable. Moxifloxacin for children is not part of standard practice.
Older Adults
Older adults are at increased risk for moxifloxacin-related adverse effects, including QT prolongation, tendinopathy, aortic aneurysm, and CNS disturbances. Renal function may decline with age, but moxifloxacin does not require dose adjustment for age alone. However, the presence of polypharmacy, electrolyte abnormalities, and cardiac disease means that moxifloxacin should be used with extra caution in this population.
Renal Impairment
No dose adjustment is required in renal impairment. However, patients with renal disease often have other risk factors, including diabetes, vascular disease, and electrolyte imbalances. Moxifloxacin is not removed significantly by hemodialysis, so supplemental doses after dialysis are not needed.
Hepatic Impairment
Mild to moderate hepatic impairment does not require dose adjustment. Severe hepatic impairment is a contraindication or strong precaution. In patients with cirrhosis, the risk of QT prolongation and other toxicities may be increased.
Monitoring During Moxifloxacin Therapy
Healthcare professionals may monitor the following parameters when clinically indicated:
- Clinical response: Resolution of fever, pain, leukocytosis, and other infection-specific signs.
- Hepatic function: Liver enzymes if hepatotoxicity is suspected or if the patient develops jaundice, nausea, or abdominal pain.
- ECG/QT interval: In patients at risk for QT prolongation or those taking other QT-prolonging drugs.
- Blood glucose: In diabetic patients, especially those on sulfonylureas or insulin.
- INR: In patients taking warfarin, especially during initiation and discontinuation of moxifloxacin.
- Microbiological response: Repeat cultures where appropriate to ensure bacterial eradication.
- Adverse reactions: Monitor for tendon pain, neuropathy symptoms, photosensitivity, and signs of C. difficile-associated diarrhea.
Routine therapeutic drug monitoring of moxifloxacin is not standard practice, but it may be considered in selected critically ill patients or those with complex pharmacokinetic alterations.
Clinical Perspective
Moxifloxacin occupies a specific niche in antimicrobial therapy. It is not a first-line drug for uncomplicated cystitis, strep throat, or routine sinusitis. It is a respiratory and mixed-infection fluoroquinolone with excellent tissue penetration and once-daily dosing. In the right patient, it can be a moxifloxacin life saving antibiotic. In the wrong patient, it can trigger a dangerous cascade of cardiac, neurologic, or musculoskeletal harm.
The clinical perspective is about balance. A patient with severe community-acquired pneumonia and beta-lactam allergy may benefit greatly from moxifloxacin. A patient with uncomplicated acute bronchitis and a normal chest radiograph should not receive it. A diabetic patient with a polymicrobial foot infection and no other oral options may need moxifloxacin’s anaerobic and Gram-positive coverage. A healthy adult with mild sinusitis should not be exposed to moxifloxacin dangerous side effects for a condition that often resolves without antibiotics.
Antimicrobial stewardship is not optional. Every unnecessary fluoroquinolone prescription contributes to resistance and exposes a patient to harm. Moxifloxacin vs levofloxacin vs ciprofloxacin comparison helps clinicians choose the right drug. Ciprofloxacin is preferred for Pseudomonas and many urinary infections. Levofloxacin is a respiratory fluoroquinolone with broader Gram-negative activity than moxifloxacin but requiring renal dose adjustment. Moxifloxacin has the best anaerobic coverage and is convenient in renal impairment, but it has the highest QT-prolongation risk among the three. When evaluating levofloxacin as an alternative, the clinical and dosing differences are not always obvious at first glance. This detailed guide breaks down levofloxacin’s specific role in respiratory and other infections: Levofloxacin Uses for Infections.
The clinical perspective also includes the responsibility to explain risks. Patients should know why moxifloxacin is being prescribed, what alternatives exist, and what symptoms require immediate medical attention. Informed consent is not only for procedures. It applies to high-risk antibiotics as well. For healthcare professionals seeking curated online earning resources, professional networking groups, and digital health communities, ssthem.xyz for Online Earning and WhatsApp Groups Links offers a starting point that complements clinical knowledge without replacing it.
For readers interested in broader studies beyond pharmacology, ssthem.com for Studies of Religions offers additional educational resources. However, this article’s focus remains evidence-based moxifloxacin information.
Question . What is moxifloxacin?
Question . What is moxifloxacin used for?
Question . How does moxifloxacin work?
Question . How long does moxifloxacin stay in the body?
Question . What is the half-life of moxifloxacin?
Question . What are common moxifloxacin side effects?
Question . What are serious moxifloxacin adverse effects?
Question . Is moxifloxacin FDA approved?
Question . What infections does moxifloxacin treat?
Question . Can moxifloxacin be used during pregnancy?
Question . Can moxifloxacin be used while breastfeeding?
Question . Can I drink alcohol with moxifloxacin?
Question. What medicines interact with moxifloxacin?
Question. What happens if I miss a dose of moxifloxacin?
Question. How should moxifloxacin be taken?
Question. Does renal impairment require dose adjustment?
Question. Does hepatic impairment affect moxifloxacin?
Question. Is moxifloxacin safe for children?
Question. Is moxifloxacin appropriate for older adults?
Question. What should clinicians monitor during moxifloxacin therapy?
Question. What are alternatives to moxifloxacin?
Question. What are major contraindications?
Question 23. How does resistance affect moxifloxacin use?
Question. How long does moxifloxacin treatment usually last?
Question. When should I seek medical attention?
5 Authentic Studies on Moxifloxacin
The following five studies are real, peer-reviewed, and clinically relevant. They are selected to illustrate moxifloxacin’s efficacy, pharmacokinetics, safety, and resistance.
Study 1
Citation: Balfour JA, Lamb HM. Moxifloxacin: a review of its clinical potential in the management of community-acquired respiratory tract infections. Drugs. 2000;59(1):115-139. doi:10.2165/00003495-200059010-00007
Study Type: Systematic review
Population: Patients with community-acquired respiratory tract infections
Intervention/Exposure: Moxifloxacin clinical and microbiological evaluation
Comparator: Other fluoroquinolones and beta-lactams
Main Outcome: Efficacy and safety summary
Key Findings: Moxifloxacin showed high clinical success rates in respiratory infections with once-daily dosing and good tissue penetration.
Clinical Significance: Provides early evidence supporting moxifloxacin’s role in respiratory infections.
Important Limitation: Review published before widespread emergence of fluoroquinolone resistance and before full recognition of serious adverse effects.
Study 2
Citation: Owens RC Jr, Ambrose PG. Antimicrobial safety: focus on fluoroquinolones. Clin Infect Dis. 2005;41(Suppl 2):S144-S157. doi:10.1086/428054
Study Type: Safety review
Population: Patients receiving fluoroquinolones
Intervention/Exposure: Safety analysis of fluoroquinolone class
Comparator: Class-wide adverse effect profiles
Main Outcome: Incidence and mechanisms of serious adverse effects
Key Findings: Fluoroquinolones, including moxifloxacin, are associated with QT prolongation, tendinopathy, dysglycemia, and CNS effects. Moxifloxacin has a higher QT risk than some class members.
Clinical Significance: Highlights the need for risk stratification before prescribing moxifloxacin.
Important Limitation: Review-level evidence; individual patient risk factors vary.
Study 3
Citation: Pépin J, Saheb N, Coulombe MA, et al. Emergence of fluoroquinolones as the predominant risk factor for Clostridium difficile-associated diarrhea: a cohort study during an epidemic in Quebec. Clin Infect Dis. 2005;41(9):1254-1260. doi:10.1086/496986
Study Type: Cohort study
Population: Hospitalized patients with C. difficile-associated diarrhea
Intervention/Exposure: Antibiotic exposure assessment
Comparator: Patients without C. difficile infection
Main Outcome: Fluoroquinolone exposure as risk factor
Key Findings: Fluoroquinolone use, including moxifloxacin, was strongly associated with epidemic C. difficile infection.
Clinical Significance: Reinforces the need for antimicrobial stewardship and C. difficile risk awareness with fluoroquinolones.
Important Limitation: Observational design with potential confounding; epidemic strain context may limit generalizability.
Study 4
Citation: Wise R, Honeybourne D. Pharmacokinetics and pharmacodynamics of moxifloxacin. Clin Microbiol Infect. 1999;5(Suppl 3):S17-S24. doi:10.1111/j.1469-0691.1999.tb00706.x
Study Type: Pharmacokinetic/pharmacodynamic study
Population: Healthy volunteers and patients with respiratory infections
Intervention/Exposure: Moxifloxacin 400 mg single and multiple doses
Comparator: None or other fluoroquinolones
Main Outcome: AUC/MIC ratios, tissue penetration, and half-life
Key Findings: Moxifloxacin achieves high epithelial lining fluid concentrations and favorable AUC/MIC ratios against S. pneumoniae.
Clinical Significance: Supports once-daily dosing and respiratory infection efficacy.
Important Limitation: Small sample sizes; PK/PD targets derived from in vitro and animal models.
Study 5
Citation: Khaliq Y, Zhanel GG. Fluoroquinolone-associated tendinopathy: a critical review of the literature. Clin Infect Dis. 2003;36(11):1404-1410. doi:10.1086/375078
Study Type: Systematic review
Population: Patients with fluoroquinolone-associated tendinopathy
Intervention/Exposure: Fluoroquinolone use, including moxifloxacin
Comparator: Not applicable (observational data)
Main Outcome: Incidence, risk factors, and characteristics of tendinopathy
Key Findings: This review solidified the link between fluoroquinolones and tendinopathy, identifying advanced age, corticosteroid use, and renal transplantation as major risk factors.
Clinical Significance: This study is foundational to the Black Box Warnings we see today. It directly informs the clinical practice of avoiding moxifloxacin in high-risk patients.
Important Limitation: Based on retrospective and observational data, which cannot establish causation with the same certainty as a randomized trial.
Authentic References
- Moxifloxacin [package insert]. Bethesda, MD: National Institutes of Health. U.S. National Library of Medicine. DailyMed.
- Bennett JE, Dolin R, Blaser MJ. Mandell, Douglas, and Bennett’s Principles and Practice of Infectious Diseases. 9th ed. Elsevier; 2019.
- Metlay JP, Waterer GW, Long AC, et al. Diagnosis and Treatment of Adults with Community-acquired Pneumonia. An Official Clinical Practice Guideline of the American Thoracic Society and Infectious Diseases Society of America. Am J Respir Crit Care Med. 2019;200(7):e45-e67.
- Centers for Disease Control and Prevention (CDC). Antibiotic Resistance Threats in the United States, 2019. U.S. Department of Health and Human Services, CDC; 2019.
- U.S. Food and Drug Administration (FDA). FDA Drug Safety Communication: FDA updates warnings for oral and injectable fluoroquinolone antibiotics due to disabling side effects. 2016.
- Tandan M, Cormican M, Vellinga A. A systematic review and meta-analysis of the effect of fluoroquinolones on the risk of aortic aneurysm and dissection. J Antimicrob Chemother. 2018;73(7):1723-1730.
- Aldred KJ, Kerns RJ, Osheroff N. Mechanism of quinolone action and resistance. Biochemistry. 2014;53(10):1565-1574.
Medical Information Disclaimer: This article is provided for educational and informational purposes only and is not intended as medical advice. It is not a substitute for professional diagnosis, treatment, or clinical judgment. The information contained herein reflects evidence from current literature and prescribing information, but clinical practice may vary based on individual patient factors, local resistance patterns, and emerging evidence. Prescription decisions must be made by a qualified healthcare professional. Patients should never self-medicate with moxifloxacin or any prescription antibiotic. If you have questions about your health or medication, consult your physician, pharmacist, or another licensed provider. If you are experiencing a medical emergency, seek immediate medical attention.

