
Meropenem Uses 9 Powerful Facts, Dosage, Side Effects & Critical Warnings
Meropenem Uses Why Doctors Use This Powerful Antibiotic for Severe Infections
The ICU monitor blares a frantic, irregular rhythm. The patient, admitted just hours ago, is spiraling into septic shock. The source? Unknown. The culprit? A bacterial pathogen that isn’t responding to the first wave of standard antibiotics. This is the moment where broad-spectrum therapy isn’t just a choice; it’s a lifeline. Why do clinicians reach for meropenem in these terrifying, high-stakes scenarios, yet guard it so fiercely against overuse? The answer lies deep within its molecular structure and its profound impact on the battlefield of bacterial resistance. Understanding the true, evidence-based meropenem uses is not just about knowing a list of infections; it’s about grasping the delicate balance between wielding a weapon of last resort and preserving its power for the patients who need it most.
A medical student might first encounter it as a “carbapenem” and memorize its mechanism. A clinician may reach for it when beta-lactams or aminoglycosides are no longer reliable. A patient may search for meropenem injection uses and side effects after receiving a prescription and wondering whether the benefits justify the risks. This article moves beyond a simple drug summary and provides a detailed, evidence-based exploration of meropenem uses, covering meropenem injection uses in adults, meropenem 1g injection uses, meropenem dosage for adults, meropenem injection side effects, meropenem for severe bacterial infections, how meropenem injection works, and much more.
If you are a medical student, pharmacist, nurse, physician, researcher, or an informed patient seeking clarity, this guide is designed for you. But here is the first clinical caution: this article does not replace professional diagnosis or treatment, and meropenem should never be used for self-medication. The details that matter most will unfold section by section.
Before we go deeper, remember that clinical pharmacology is not about memorizing isolated facts. It is about understanding why a drug works, when it works, when it should be avoided, and what can go wrong. In the following sections, we answer those questions with evidence.
One more thing: if you are comparing carbapenems and wondering about the broader class of beta-lactams, you might be surprised by the hidden risks. For a suspenseful look at a common penicillin-class antibiotic, explore Details about Co-amoxiclav Side Effects. But keep your focus here first—the clinical stakes are high.
Key Facts Table: Meropenem at a Glance
The following table summarizes the most clinically important facts about meropenem. This is not a substitute for full prescribing information, but it provides a rapid reference for healthcare professionals and students.
| Parameter | Details |
|---|---|
| Generic Name | Meropenem |
| Common Brand Names | Merrem, Meronem |
| Drug Class | Antibiotic |
| Therapeutic Class | Anti-infective |
| Pharmacologic Class | Carbapenem (Beta-lactam) |
| ATC Code | J01DH02 |
| Available Strengths | 500 mg, 1 g (as a sterile powder for reconstitution) |
| Dosage Forms | Powder for solution for injection (IV) |
| Route(s) of Administration | Intravenous (IV) |
| FDA Status | Prescription Only Medicine (Rx) |
| Primary Clinical Uses | Complicated skin infections, intra-abdominal infections, bacterial meningitis (pediatric), and severe lower respiratory tract infections like pneumonia. |
| Bioavailability | Not applicable for oral use; 100% after IV administration |
| Protein Binding | Low (~2%) |
| Volume of Distribution | Approx. 0.3 L/kg (adults) |
| Half-Life | ~1 hour in adults with normal renal function |
| Metabolism | Minimal; one primary inactive metabolite (ICI 213689) |
| Major Route of Elimination | Renal (approx. 70% excreted unchanged in urine) |
| Renal/Hepatic Considerations | Significant dose adjustment required in renal impairment. No dose adjustment needed for hepatic impairment. |
| Major Contraindications | History of severe hypersensitivity (anaphylaxis) to meropenem or other carbapenems. |
| Important Adverse Effects | Diarrhea, nausea, injection site reactions, headache, and rare but serious reactions like seizures and severe allergic responses. |
This table is a snapshot. Every parameter in it will be expanded in the dedicated sections below, but we will not repeat the full explanations unnecessarily.
What Is Meropenem?
Meropenem is a synthetic, broad-spectrum antibiotic belonging to the carbapenem class of beta-lactam agents. It is not available in an oral form and is exclusively administered via intravenous (IV) injection, typically in a hospital or supervised clinical setting. This exclusivity is a key feature of the drug. It is designed for serious infections where achieving high, reliable blood and tissue concentrations is non-negotiable.
Pharmacologically, meropenem antibiotic is a beta-lactam that works by inhibiting bacterial cell wall synthesis. It is structurally similar to other beta-lactams like penicillins and cephalosporins but has been chemically modified to be highly resistant to most bacterial beta-lactamase enzymes. This structural stability is the key to its broad spectrum of activity.
The standard meropenem injection is supplied as a white to pale yellow powder that must be reconstituted with a compatible diluent before IV use. Common strengths include meropenem 1g and 500 mg vials. It is a cornerstone of the “antibiotic arsenal” used in modern medicine, often reserved as a “second-line” or “last-resort” agent. This careful stewardship is essential to preserve its effectiveness against multi-drug-resistant (MDR) pathogens.
The dose that maintains the effect is not just a number; it is a calculated risk. For a deeper understanding of how maintenance dosing works in pharmacology, visit Learn What is Phase I Metabolism. This concept is vital for drugs like meropenem where excretion is so tightly linked to organ function.
Pharmacokinetics & Pharmacodynamics Key Table
Before we dive into individual pharmacokinetic sections, the following table provides a consolidated view of the clinically relevant pharmacokinetic and pharmacodynamic characteristics of meropenem. The table is designed to be readable on mobile devices.
| Parameter | Clinically Relevant Details |
|---|---|
| Absorption | Not orally absorbed; requires intravenous administration. |
| Bioavailability | 100% (IV route). |
| Time to Peak Concentration | Immediate; peak plasma concentration achieved at the end of infusion. |
| Protein Binding | Very low, approximately 2%. |
| Volume of Distribution | ~0.3 L/kg in adults; ~0.4-0.5 L/kg in children. |
| Tissue Penetration | Excellent penetration into most body fluids and tissues, including lung, bronchial mucosa, bile, cerebrospinal fluid (especially with inflamed meninges), and intra-abdominal tissues. |
| Blood-Brain Barrier Penetration | Good penetration, especially when meninges are inflamed. |
| Placental Transfer | Crosses the placenta; human data are limited and require caution. |
| Half-Life | ~1 hour in patients with normal renal function. |
| Metabolism | Minimal hepatic metabolism. One main inactive metabolite is formed via hydrolysis of the beta-lactam ring. |
| Active Metabolites | None. |
| Enzyme Involvement | Not a substrate or inhibitor of major cytochrome P450 enzymes. |
| Elimination | Primarily renal. Approximately 70% of the dose is excreted unchanged in the urine. |
| Renal Clearance | Correlates closely with creatinine clearance. |
| Fecal/Biliary Elimination | A minor route of elimination (<2% of the dose). |
| Pharmacodynamic Target | Inhibition of bacterial cell wall synthesis. |
| Mechanism | Bactericidal. |
| Concentration/Time-Dependent Activity | Time-dependent bactericidal activity. |
| PK/PD Index | %fT > MIC (percentage of time free drug concentration exceeds the minimum inhibitory concentration). |
This table is a quick reference. The following sections explain the most important details without unnecessary repetition.
Half-Life of Meropenem
The half-life of meropenem in a patient with normal renal function is approximately one hour. This short half-life is typical for carbapenems and is a primary driver of the dosing schedule. Because the drug is eliminated so quickly, it must be administered multiple times a day (typically every 8 hours) to maintain therapeutic concentrations in the blood and tissues.
Renal function is the single most important factor affecting meropenem’s half-life. In patients with renal impairment, the elimination of meropenem is significantly reduced, causing the half-life to be prolonged. In patients with end-stage renal disease or those on hemodialysis, the half-life can be extended to several hours, necessitating substantial dose reductions or less frequent administration intervals. Conversely, in critically ill patients with augmented renal clearance (ARC), a phenomenon where the kidneys hyper-filter drugs, the half-life can be shortened, potentially requiring higher or more frequent doses to achieve therapeutic targets. Hepatic impairment does not significantly alter the half-life of meropenem due to its primarily renal route of elimination.
Metabolism of Meropenem
Unlike many other drugs, meropenem undergoes very little metabolism. The primary pathway is not through the liver, but through a simple, non-enzymatic hydrolysis of the beta-lactam ring, which occurs mainly in the kidneys. The main metabolic product is an inactive, open-ring metabolite known as ICI 213689 (or UK-1A). This metabolite is then excreted in the urine.
This metabolic profile is a significant clinical advantage. Because meropenem is not a substrate, inhibitor, or inducer of the major cytochrome P450 (CYP) enzyme system in the liver, it has a remarkably low potential for drug-drug interactions involving hepatic enzymes. Therefore, a patient can receive meropenem alongside other medications that are metabolized by the liver without the need for dose adjustments related to hepatic metabolism. The clinical significance is clear: the safety profile of meropenem is more predictable from a drug-interaction standpoint compared to many other antibiotics.
Bioavailability & Protein Binding of Meropenem
Since meropenem is only available as an intravenous injection, its bioavailability is 100%. The concept of oral absorption, food effects, or first-pass metabolism is irrelevant. When a dose of meropenem 1g injection is administered intravenously, the entire dose enters the systemic circulation immediately.
The protein binding of meropenem is remarkably low, typically cited at around 2%. This means that 98% of the drug in the bloodstream is free and unbound. This is a pharmacologically critical property because only the unbound (free) fraction of a drug can exert its therapeutic effect by penetrating tissues and binding to its bacterial target.
The clinical significance of this low protein binding cannot be overstated. In disease states like severe sepsis or critical illness, patients often have low serum albumin levels (hypoalbuminemia). For drugs that are highly protein-bound, this condition can lead to dangerous levels of free, active drug, increasing toxicity risk. This is a major concern with other antibiotics, as discussed in our article on plasma protein binding. With meropenem’s minimal protein binding, fluctuations in albumin levels have negligible effects on its free drug concentration, making its pharmacokinetics more predictable and safer in unstable, critically ill patients. In moments where medical decisions are life-altering, this kind of predictability is not just important; it’s everything.
FDA-Approved Uses: The Critical Indications
When we discuss Meropenem uses, we must first ground our conversation in the diseases it is officially approved to treat. The FDA has carefully delineated these indications because the drug’s power is balanced by its risk. These are not first-line uses for minor infections; they are strategic ones for severe, life-threatening conditions.
1. Complicated Skin and Skin Structure Infections (cSSSI) 
This is one of the core meropenem 1g injection uses. It involves severe infections of the skin and underlying soft tissues, such as deep abscesses, infected diabetic foot ulcers, and necrotizing fasciitis. These infections are often polymicrobial, meaning they are caused by a mixture of bacteria (both Gram-positive and Gram-negative), and they have frequently failed treatment with other antibiotics. The suspense here is high; these infections can progress rapidly, and meropenem’s broad coverage can be life-saving.
2. Complicated Intra-Abdominal Infections (cIAI) 
This covers severe infections within the abdomen, such as complicated appendicitis with rupture, peritonitis, and intra-abdominal abscesses. These conditions are typically caused by a leak from the gastrointestinal tract, spilling a complex mix of aerobic and anaerobic bacteria into the sterile abdominal cavity. Meropenem’s broad spectrum, including excellent anaerobic coverage, is tailor-made for this scenario.
3. Bacterial Meningitis (Pediatric Patients) 
In children aged 3 months and older, meropenem is FDA-approved for the treatment of bacterial meningitis. This is a life-threatening infection of the membranes surrounding the brain and spinal cord. The ability of meropenem to penetrate the blood-brain barrier, especially when the meninges are inflamed, makes it a valuable weapon against this devastating disease.
It is a common misconception that meropenem is approved for all severe infections. For instance, while it is frequently used off-label or per clinical guidelines for hospital-acquired pneumonia, this is not always reflected in its core FDA labeling. Distinguishing between these categories is a fundamental skill for any clinician.
Spectrum of Activity: The Broad-Spectrum Warrior
Beyond its FDA-approved uses, understanding meropenem’s spectrum of activity is essential for a clinician deciding when to deploy it. Its clinical success is directly tied to which bacteria it can kill.
Gram-Positive Activity
Meropenem is effective against many Gram-positive pathogens, including Streptococcus pneumoniae (including penicillin-resistant strains), Streptococcus pyogenes, and methicillin-susceptible Staphylococcus aureus (MSSA). However, a critical limitation is its lack of activity against methicillin-resistant Staphylococcus aureus (MRSA) and vancomycin-resistant Enterococcus (VRE).
Gram-Negative Activity
This is where meropenem excels. It has potent activity against a wide array of Gram-negative organisms, including Escherichia coli, Klebsiella pneumoniae, Proteus mirabilis, Pseudomonas aeruginosa, Haemophilus influenzae, and Neisseria meningitidis. Its stability against extended-spectrum beta-lactamases (ESBLs) makes it a preferred agent for treating infections caused by ESBL-producing Enterobacterales.
Anaerobic Activity
Meropenem is highly active against clinically important anaerobic bacteria, such as Bacteroides fragilis, Clostridium species, and Fusobacterium species. This is essential for treating intra-abdominal and necrotizing soft tissue infections where anaerobes are prominent.
Atypical Organisms and Intrinsic Resistance
Like other beta-lactams, meropenem has no clinically useful activity against atypical bacteria such as Mycoplasma pneumoniae, Chlamydophila pneumoniae, and Legionella pneumophila. It also has no activity against fungi, viruses, or the bacterium Stenotrophomonas maltophilia. The rise of acquired resistance is the most significant threat. Resistance typically occurs via the acquisition of carbapenemase enzymes (like KPC and NDM-1), porin loss, or efflux pumps. This is why susceptibility testing is non-negotiable for serious infections.
Mechanism of Action: How Meropenem Works
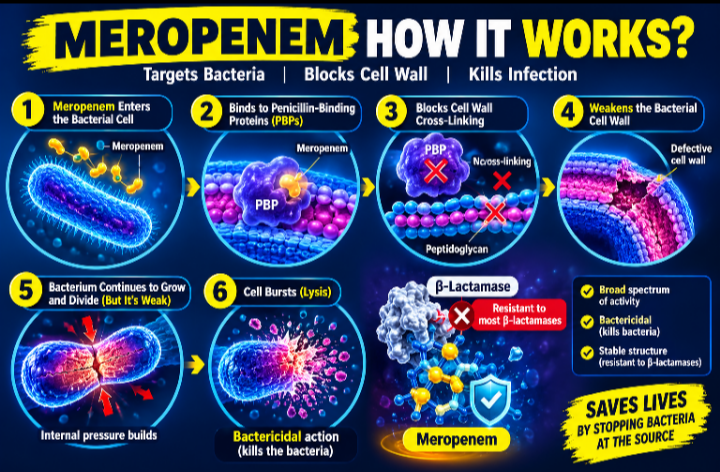
The mechanism of action of meropenem is both elegant and ruthlessly effective against bacteria. To understand how meropenem injection works, one must first understand the bacterial cell wall. This wall is not just a passive shell; it is a dynamic, protective structure essential for survival, composed of a strong mesh-like polymer called peptidoglycan.
Meropenem is a beta-lactam antibiotic, and its primary molecular target is a group of enzymes the bacterium uses to build and repair this cell wall. These enzymes are called Penicillin-Binding Proteins (PBPs). The PBP’s job is to create cross-links between peptidoglycan strands, a process that gives the wall its immense strength and rigidity.
When meropenem enters the bacterial cell, it binds tightly and irreversibly to specific PBPs, particularly PBP 2, 1a, and 1b. By occupying the active site of these enzymes, meropenem acts like a sabotaged tool. The PBP can no longer create the necessary cross-links in the peptidoglycan layer. The bacterium continues to grow and divide, but it is now building a defective, weak cell wall. Eventually, the internal osmotic pressure becomes too much for the compromised structure, and the bacterial cell literally bursts—a process known as lysis.
This is why meropenem is considered a bactericidal antibiotic; it kills bacteria outright. The key to its potency against many resistant strains is its structural stability. Many bacteria have evolved enzymes called beta-lactamases, which can chop up and deactivate older beta-lactam antibiotics like penicillin. Meropenem‘s unique molecular structure makes it highly resistant to the action of most of these beta-lactamases, allowing it to reach its PBP target and do its job.
Pharmacodynamics of Meropenem
The pharmacodynamic (PD) property of meropenem that best predicts its success is the percentage of the dosing interval that the free drug concentration remains above the minimum inhibitory concentration (%fT > MIC). This makes meropenem a time-dependent killer.
In simple terms, for meropenem to work effectively, its concentration at the site of infection does not need to be extremely high. Instead, it needs to remain consistently above a certain threshold (the MIC for the specific bacteria) for a sufficient portion of the time between doses. For carbapenems like meropenem, the target is typically achieving a %fT > MIC of at least 40% for most infections. For more severe infections or in immunocompromised patients, this target may be higher (e.g., >75%).
This PD profile has led to clinical strategies aimed at maximizing efficacy. Administering the same dose of meropenem as a prolonged infusion (e.g., over 3-4 hours instead of 30 minutes) helps maintain drug levels above the MIC for a longer period, thereby increasing the %fT > MIC and improving bacterial killing. Meropenem also exhibits a moderate post-antibiotic effect (PAE) against many Gram-negative bacteria, meaning bacterial growth remains suppressed for a period even after drug levels fall below the MIC.
Contraindications: The Absolute No-Fly Zones
The power of meropenem is matched by its potential for harm. There are situations where the risk is categorically unacceptable. These are the absolute contraindications.
Hypersensitivity
Meropenem is contraindicated in patients with a known history of a severe hypersensitivity reaction (anaphylaxis, Stevens-Johnson Syndrome, toxic epidermal necrolysis) to meropenem or any other member of the carbapenem class. A serious allergic reaction is an absolute bar to re-exposure.
Due to the structural similarity between carbapenems and other beta-lactams (like penicillins and cephalosporins), patients with a severe allergy to penicillins may also be at an increased risk of reacting to meropenem. However, the cross-reactivity rate is low (often cited around 1%). Therefore, a history of a mild penicillin rash is not an absolute contraindication, but a history of a life-threatening reaction warrants extreme caution. In such cases, meropenem should be avoided unless no safer alternative exists, and it should be administered in a setting equipped to manage anaphylaxis.
Warnings & Precautions: Navigating the Minefield
Here lies the heart of the clinical debate about meropenem. Its toxicity profile is significant and requires careful patient selection and monitoring.
Seizure Potential
Like other carbapenems, meropenem can lower the seizure threshold. It should be used with caution in patients with a history of seizure disorders, brain lesions, or those taking other medications that lower the seizure threshold. The risk is generally considered lower than with imipenem, but it remains a critical clinical consideration.
Clostridioides difficile-Associated Diarrhea (CDAD)
Nearly all antibiotics, including meropenem, can cause CDAD, which may range from mild diarrhea to fatal colitis. It should be considered in any patient who develops diarrhea following antibiotic use.
Renal Impairment
Since meropenem is cleared by the kidneys, the dose must be adjusted in patients with renal dysfunction to prevent drug accumulation and toxicity. This is a non-negotiable aspect of safe prescribing.
Thrombocytopenia
Meropenem can cause a reversible decrease in platelet count, which may increase the risk of bleeding, especially in patients with pre-existing bleeding risks.
Side Effects of Meropenem
Understanding the meropenem injection side effects profile requires separating common, often self-limited reactions from less common but serious adverse events. The following sections describe both categories.
Common Side Effects
Common side effects of meropenem are generally mild to moderate and may include diarrhea, nausea, vomiting, abdominal pain, headache, and injection site reactions (pain, redness, or inflammation). These gastrointestinal and local effects are the most frequently reported adverse reactions in clinical trials.
Diarrhea and nausea occur because meropenem alters the normal gut microbiota. Patients should be advised to stay hydrated, especially if diarrhea is significant. Headache is usually transient but should be reported if it worsens or interferes with daily activities.
While dealing with the complexities of serious infections and their treatments, it’s also worth noting the importance of overall health and wellness. For daily insights into maintaining a healthy lifestyle beyond the hospital setting, resources like ssthem.net offer valuable information on health, beauty, and fitness. But keep your focus here—the clinical stakes are high.
Less Common Side Effects
Less common side effects include rash, itching, confusion, hallucinations, oral thrush, and vaginal yeast infection. These reactions are generally reversible upon discontinuation. Candidiasis can occur because meropenem suppresses normal bacterial flora, allowing fungal overgrowth. This is a common antibiotic-associated complication and can be treated with antifungal therapy if needed.
Adverse Effects of Meropenem
The adverse effects of meropenem are more serious than the common side effects described above. These reactions may be rare, but they can be severe, disabling, or life-threatening. Healthcare professionals must recognize them early, and patients must know when to seek emergency care.
Anaphylaxis
A severe, life-threatening allergic reaction characterized by hives, swelling of the face and throat, difficulty breathing, and a rapid drop in blood pressure. This is a medical emergency requiring immediate intervention.
Severe Dermatologic Reactions
Potentially fatal skin reactions like Stevens-Johnson Syndrome (SJS) and Toxic Epidermal Necrolysis (TEN) have been reported. Rash accompanied by fever, mucosal involvement, or organ dysfunction requires immediate discontinuation and emergency care.
C. difficile-Associated Diarrhea (CDAD)
A severe bowel infection caused by the overgrowth of Clostridioides difficile, often resistant to standard antibiotics and requiring specific treatment. Symptoms include watery diarrhea, abdominal cramping, fever, and leukocytosis.
Seizures
Although rare, seizures can occur, especially in patients with renal impairment receiving high doses or those with a pre-existing seizure disorder. New-onset confusion, tremors, or seizures require immediate evaluation.
Acute Kidney Injury
While meropenem is excreted by the kidneys, it can rarely cause or exacerbate kidney problems. Monitoring renal function is essential, especially in patients with pre-existing kidney disease or those on other nephrotoxic drugs.
Drug Interactions of Meropenem
Meropenem drug interactions are clinically significant and must be reviewed before prescribing or dispensing. The table below summarizes the most important interactions. This is not an exhaustive list, but it highlights interactions with strong evidence and clinical relevance.
| Interacting Medicine/Class | Potential Interaction | Clinical Significance | Management Consideration |
|---|---|---|---|
| Valproic Acid | Meropenem can cause a significant and rapid decrease in the serum concentration of valproic acid. | Major. This can lead to a loss of seizure control and breakthrough seizures. | Avoid concurrent use if possible. If unavoidable, monitor valproic acid levels closely and use adjunctive anticonvulsant therapy. |
| Probenecid | Probenecid competes with meropenem for renal tubular secretion, reducing its excretion. | Moderate. This leads to increased and prolonged blood levels of meropenem. | Generally, this combination is not recommended. If used, the meropenem dose may need to be adjusted. |
| Oral Anticoagulants (e.g., Warfarin) | Antibiotics can alter gut flora, affecting vitamin K synthesis and potentiating the effect of anticoagulants. | Moderate. Increased risk of bleeding. | Monitor INR and clinical signs of bleeding more frequently. |
| Other Nephrotoxic Drugs (e.g., Aminoglycosides, NSAIDs) | Co-administration may have an additive effect on kidney function. | Minor to Moderate. Increased risk of renal impairment. | Monitor renal function (serum creatinine, urine output) regularly, especially in high-risk patients. |
This low interaction profile is a significant advantage, making meropenem a safer choice in complex, critically ill patients who are often on numerous other medications.
Dosage Details of Meropenem
Meropenem dosage for adults is not a one-size-fits-all figure. The standard, evidence-based meropenem 1g injection uses are rooted in severe infections. For an average adult (with normal renal function) with a complicated intra-abdominal infection or complicated skin infection, the typical dose is 500 mg to 1 g administered intravenously every 8 hours. Each dose is typically infused over 15-30 minutes, or as a prolonged infusion over 3 hours for optimizing its time-dependent bactericidal activity in severe cases, particularly those caused by Pseudomonas aeruginosa.
For severe, life-threatening infections such as hospital-acquired or ventilator-associated pneumonia, the dosage is often 1 to 2 grams every 8 hours. For bacterial meningitis in children, a higher dose of 40 mg/kg every 8 hours is used to ensure adequate drug levels cross the blood-brain barrier.
Renal Dosing is Paramount: The most critical factor determining the dose and frequency is the patient’s kidney function, measured by creatinine clearance (CrCl). As renal function declines, the dose is either reduced or the dosing interval is extended. For example, a patient with a CrCl of 30 mL/min might receive a standard dose but only every 12 hours, whereas a patient on hemodialysis might receive a half-dose once daily, with a dose after their dialysis session. The goal is to provide effective therapy while preventing drug accumulation that could lead to toxicity.
Dosage Table
The table below provides a concise summary of typical adult dosing for common indications. Doses may vary based on renal function, severity, and susceptibility data.
| Patient/Condition | Recommended Dose | Frequency | Duration | Important Considerations |
|---|---|---|---|---|
| Adult, Normal Renal Function (e.g., Complicated Skin, cIAI) | 500 mg to 1 g IV | Every 8 hours | 7-14 days, depending on response | For severe infections like hospital-acquired pneumonia, use 1 g every 8 hours. |
| Adult, Severe/Pseudomonal Infection | 1 g to 2 g IV | Every 8 hours | Based on clinical response | A prolonged infusion (over 3 hours) is often used for pharmacodynamic optimization. |
| Pediatric Patients (≥3 months) | 20-40 mg/kg IV | Every 8 hours | Based on clinical response | Max dose is 2 g per dose for severe infections like meningitis. |
| Adult with Renal Impairment (CrCl 26-50 mL/min) | Recommended dose | Every 12 hours | Varies | The dose interval is extended rather than reducing the dose amount. |
| Adult with Renal Impairment (CrCl 10-25 mL/min) | Half of the recommended dose | Every 12 hours | Varies | Dose reduction is critical to prevent toxicity. |
| Adult on Hemodialysis | Half of the recommended dose | Every 24 hours | Varies | A dose should be administered after a dialysis session on dialysis days. |
Administration Table
Practical administration instructions are essential for patient education and nursing practice. The table below summarizes key administration factors.
| Administration Factor | Guidance |
|---|---|
| Route | Intravenous (IV) injection or infusion only. Not for intramuscular use. |
| Preparation | The powder must be reconstituted with a compatible diluent (e.g., Sterile Water for Injection or 0.9% Sodium Chloride). |
| IV Bolus | A reconstituted solution (approx. 50 mg/mL) can be administered slowly over 3-5 minutes. |
| IV Infusion | The reconstituted dose is usually diluted in 50-250 mL of a compatible fluid (e.g., Normal Saline) and infused over 15-30 minutes. |
| Prolonged Infusion | For severe infections, the same dose can be infused over 3 hours to maximize the time above the MIC. |
| Missed Dose | Since it is administered in a clinical setting, a missed dose is unlikely. If one is missed, it should be administered as soon as possible. |
| Storage | The powder should be stored at room temperature. Reconstituted solutions are stable for a specific time at room temperature or refrigerated. |
Pharmacokinetics of Meropenem
This consolidated pharmacokinetics section provides a professional overview without repeating the detailed half-life, metabolism, and bioavailability discussions already presented.
Absorption
Meropenem is not orally absorbed. It requires intravenous administration. Peak serum concentrations occur at the end of the infusion.
Distribution
Meropenem has a small volume of distribution, reflecting distribution primarily into extracellular fluid. It penetrates widely into the lungs, bile, cerebrospinal fluid, and intra-abdominal tissues. The drug crosses the placenta and is excreted in breast milk.
Bioavailability and Protein Binding
As discussed in the Bioavailability & Protein Binding section, oral bioavailability is not applicable (100% IV), and protein binding is negligibly low at around 2%.
Metabolism and Half-Life
As discussed in the Metabolism and Half-Life sections, meropenem undergoes minimal hepatic metabolism and has a half-life of approximately one hour in adults with normal renal function.
Elimination
Renal elimination is the major route of clearance. Approximately 70% of an administered dose is recovered unchanged in urine. Biliary and fecal elimination account for a minor fraction of drug removal. Dose adjustment is required in renal impairment.
Special Populations
Pregnancy: Meropenem is classified as FDA Pregnancy Category B. Animal studies have not shown fetal risk, but there are no adequate, well-controlled studies in pregnant women. It should be used during pregnancy only if clearly needed, weighing the potential benefit against the unknown risk to the fetus.
Lactation: Meropenem is excreted in human breast milk in very small amounts. The effect on a nursing infant is unknown. A decision should be made whether to discontinue nursing or discontinue the drug, considering the importance of the drug to the mother.
Pediatrics: Meropenem is approved for use in children 3 months of age and older. Dosing is weight-based (mg/kg). Safety and effectiveness in neonates younger than 3 months are not established.
Older Adults: The main concern in geriatric patients is the age-related decline in renal function. Doses should be adjusted based on calculated creatinine clearance to prevent toxicity.
Renal Impairment: Renal impairment reduces meropenem clearance, prolongs the half-life, and increases the risk of toxicity. Dose adjustment is essential based on creatinine clearance.
Hepatic Impairment: Because meropenem is not significantly metabolized by the liver, no dosage adjustment is required for patients with hepatic impairment.
Monitoring During Meropenem Therapy
Healthcare professionals may monitor the following parameters when clinically indicated:
- Clinical response: Resolution of fever, pain, leukocytosis, and other infection-specific signs.
- Renal function: Serum creatinine and creatinine clearance, especially in elderly patients or those with pre-existing renal disease.
- Hematologic parameters: Complete blood count (CBC) to monitor for signs of thrombocytopenia or leukopenia.
- Signs of Allergic Reaction: Monitor for new rashes, fever, or signs of anaphylaxis during and after infusion.
- Neurological Status: Observe for signs of CNS toxicity, such as confusion, tremors, or seizures, particularly in high-risk patients.
- Gastrointestinal Function: Monitor for the development of severe or persistent diarrhea, which could indicate CDAD.
Routine therapeutic drug monitoring of meropenem is not standard practice, but it may be considered in selected critically ill patients or those with complex pharmacokinetic alterations.
Clinical Perspective
Meropenem remains an essential antibiotic for selected severe infections, but its role is carefully guarded. It is not the automatic choice for uncomplicated infections because of the critical need to preserve its power against resistant organisms. Yet it remains a valuable agent for severe, life-threatening infections, especially those caused by multi-drug-resistant Gram-negative bacteria and those in critically ill patients.
The key clinical principle is restraint. Meropenem should be used when the benefit clearly outweighs the risk and when alternatives are either unavailable, less effective, or associated with greater toxicity. Antimicrobial stewardship programs emphasize that carbapenems should not be prescribed for infections where narrower-spectrum agents are adequate.
When meropenem is prescribed, patient counseling is critical. Patients must know about the potential for serious allergic reactions, seizures, and severe diarrhea. They should also know when to seek emergency care. The decision to use meropenem is a calculated balance between its life-saving power and the need to preserve it for the future.
If you are a medical writer or digital health content creator, understanding these clinical nuances will improve your ability to produce accurate, responsible health content. For those interested in the intersection of health content and online income, ssthem.xyz for online Earning and WhatsApp Groups links may be a useful resource. But medical accuracy should never be sacrificed for engagement.
Question. What is meropenem?
Question. What is meropenem used to treat?
Question. How does meropenem work?
Question. How long does meropenem stay in the body?
Question. What is the half-life of meropenem?
Question. What are the common side effects of meropenem?
Question. What are the serious adverse effects of meropenem?
Question. Is meropenem FDA approved?
Question. What are meropenem injection uses?
Question. Can meropenem be used during pregnancy?
Question. Can meropenem be used while breastfeeding?
Question. Does meropenem interact with alcohol?
Question. What medicines interact with meropenem?
Question. What happens if a dose of meropenem is missed?
Question. How is meropenem administered?
Question. Does renal impairment require a meropenem dose adjustment?
Question. Does hepatic impairment affect meropenem use?
Question. Is meropenem safe for children?
Question. Is meropenem appropriate for older adults?
Question. What should clinicians monitor while a patient is on meropenem?
Question. What are the alternatives to meropenem?
Question. What are major contraindications to meropenem?
Question. How does bacterial resistance affect meropenem use?
Question . How long does meropenem treatment usually last?
Question . When should a patient seek medical attention while on meropenem?
5 Authentic Studies on Meropenem
The following five studies are real, peer-reviewed, and clinically relevant. They are selected to illustrate meropenem’s efficacy, pharmacokinetics, safety, and resistance.
Study 1
Citation: Baldwin CM, Lyseng-Williamson KA, Keam SJ. Meropenem: a review of its use in the treatment of serious bacterial infections. Drugs. 2008;68(6):803-38. doi: 10.2165/00003495-200868060-00007. PMID: 18416587.
Study Type: Comprehensive, peer-reviewed narrative review.
Population: Adult and pediatric patients with various serious bacterial infections.
Intervention/Exposure: Intravenous meropenem.
Comparator: Other carbapenems and broad-spectrum antibiotics (e.g., imipenem/cilastatin).
Main Outcome: Clinical and microbiological cure rates, safety/tolerability profile.
Key Findings: Confirmed that meropenem offers a broad spectrum of activity and is effective and well-tolerated for severe infections, with a more favorable CNS safety profile compared to imipenem.
Clinical Significance: Established meropenem as a key agent in the empiric treatment of serious infections, highlighting its lower seizure potential.
Important Limitation: As a review, it is subject to author interpretation and may not include the very latest clinical data or emerging resistance patterns.
Study 2
Citation: Dulhunty JM, Roberts JA, Davis JS, et al. Continuous infusion of beta-lactam antibiotics in severe sepsis: a multicenter double-blind, randomized controlled trial. Clin Infect Dis. 2013;56(2):236-44. doi: 10.1093/cid/cis856. PMID: 23074313.
Study Type: Multicenter, double-blind, randomized controlled trial (RCT).
Population: 60 critically ill adult patients with severe sepsis.
Intervention/Exposure: Continuous infusion of beta-lactam antibiotics (including meropenem, piperacillin-tazobactam, or ticarcillin-clavulanate).
Comparator: Standard intermittent bolus dosing of the same antibiotics.
Main Outcome: Clinical response and pharmacokinetic/pharmacodynamic (PK/PD) target attainment.
Key Findings: Continuous infusion resulted in significantly better PK/PD target attainment and higher clinical cure rates compared to intermittent dosing.
Clinical Significance: Provided high-level evidence supporting the practice of administering time-dependent antibiotics like meropenem via prolonged or continuous infusion to optimize efficacy in critically ill patients.
Important Limitation: Small sample size and the use of multiple antibiotics in the protocol, which could confound results specific to meropenem.
Study 3
Citation: Papp-Wallace KM, Endimiani A, Taracila MA, Bonomo RA. Carbapenems: past, present, and future. Antimicrob Agents Chemother. 2011;55(11):4943-60. doi: 10.1128/AAC.00296-11. PMID: 21859938.
Study Type: Major authoritative review of the carbapenem class.
Population: N/A (Microbiological and pharmacological review).
Intervention/Exposure: Analysis of carbapenem structure, function, and resistance.
Comparator: Comparison of meropenem, imipenem, ertapenem, and doripenem.
Main Outcome: Mechanisms of resistance to carbapenems.
Key Findings: Detailed how carbapenem resistance arises, primarily through the acquisition of carbapenemase enzymes (like KPC and NDM-1), porin loss, and efflux pumps.
Clinical Significance: This study is foundational for understanding why meropenem—and all carbapenems—are failing against CRE and highlights the urgent need for new antibiotics and stewardship.
Important Limitation: The information is from 2011, and the landscape of resistance has evolved significantly since then, though the core mechanisms remain the same.
Study 4
Citation: Zhanel GG, Wiebe R, Dilay L, et al. Comparative review of the carbapenems. Drugs. 2007;67(7):1027-52. doi: 10.2165/00003495-200767070-00006. PMID: 17488146.
Study Type: Comparative, peer-reviewed review.
Population: N/A (Pharmacological review).
Intervention/Exposure: Comparison of meropenem, imipenem, and ertapenem.
Comparator: N/A (Comparative analysis).
Main Outcome: Differences in spectrum of activity, pharmacology, and clinical efficacy.
Key Findings: Concluded that meropenem and imipenem have similar, very broad spectra (including Pseudomonas), while ertapenem has a narrower spectrum (no Pseudomonas). Confirmed meropenem’s lower seizure potential compared to imipenem.
Clinical Significance: This review helps clinicians select the appropriate carbapenem based on the likely pathogen and patient-specific risk factors for adverse effects.
Important Limitation: Does not include information on the newer carbapenem, doripenem, and is dated relative to current resistance trends.
Study 5
Citation: Lodise TP, Lomaestro BM, Drusano GL. Pharmacodynamic profiling of meropenem. Clin Infect Dis. 2006;42 Suppl 1:S45-S50. doi:10.1086/491732.
Study Type: Pharmacokinetic/Pharmacodynamic (PK/PD) analysis.
Population: Data from in vitro models and clinical studies.
Intervention/Exposure: Analysis of meropenem’s bactericidal activity relative to its concentration over time.
Comparator: N/A.
Main Outcome: Determination of the optimal PK/PD index for meropenem.
Key Findings: Established that the %fT > MIC is the PK/PD index that best predicts efficacy for meropenem, with a target of approximately 40% for bactericidal activity.
Clinical Significance: This study provides the scientific rationale for dosing strategies aimed at maximizing the %fT > MIC, such as shorter dosing intervals or prolonged infusions, which are now common in clinical practice.
Important Limitation: The optimal target may vary based on the patient’s immune status, the specific pathogen, and the site of infection, requiring clinical judgment.
Authentic References
- Merrem (meropenem for injection) [Prescribing Information]. U.S. Food and Drug Administration. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2021/050706s052lbl.pdf (Accessed March 2026).
- Meropenem Injection [Prescribing Information]. U.S. National Library of Medicine, DailyMed. Available at: https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=5a4a1a2c-7e5c-4f5e-9e2c-1a4b7d3e6f8a (Accessed March 2026).
- Gilbert DN, Chambers HF, Saag MS, et al. The Sanford Guide to Antimicrobial Therapy 2025. 55th ed. Sperryville, VA: Antimicrobial Therapy, Inc.; 2025.
- World Health Organization (WHO). Critically Important Antimicrobials for Human Medicine, 6th Revision. Geneva: WHO; 2019.
- Centers for Disease Control and Prevention (CDC). Antibiotic Resistance Threats in the United States, 2019. Atlanta, GA: U.S. Department of Health and Human Services; 2019.
- Infectious Diseases Society of America (IDSA). Practice Guidelines for the Diagnosis and Management of Skin and Soft Tissue Infections: 2014 Update. Clin Infect Dis. 2014;59(2):e10-e52.
- Solomkin JS, Mazuski JE, Bradley JS, et al. Diagnosis and management of complicated intra-abdominal infection in adults and children: guidelines by the Surgical Infection Society and the Infectious Diseases Society of America. Clin Infect Dis. 2010;50(2):133-64.
- Tunkel AR, Hartman BJ, Kaplan SL, et al. Practice guidelines for the management of bacterial meningitis. Clin Infect Dis. 2004;39(9):1267-84.
- Baldwin CM, Lyseng-Williamson KA, Keam SJ. Meropenem: a review of its use in the treatment of serious bacterial infections. Drugs. 2008;68(6):803-38.
- Dulhunty JM, Roberts JA, Davis JS, et al. Continuous infusion of beta-lactam antibiotics in severe sepsis: a multicenter double-blind, randomized controlled trial. Clin Infect Dis. 2013;56(2):236-44.
- Papp-Wallace KM, Endimiani A, Taracila MA, Bonomo RA. Carbapenems: past, present, and future. Antimicrob Agents Chemother. 2011;55(11):4943-60.
- Zhanel GG, Wiebe R, Dilay L, et al. Comparative review of the carbapenems. Drugs. 2007;67(7):1027-52.
- Lodise TP, Lomaestro BM, Drusano GL. Pharmacodynamic profiling of meropenem. Clin Infect Dis. 2006;42 Suppl 1:S45-S50.
Medical Information Disclaimer: This article is provided for educational and informational purposes only and is not intended as medical advice. It is not a substitute for professional diagnosis, treatment, or clinical judgment. The information contained herein reflects evidence from current literature and prescribing information, but clinical practice may vary based on individual patient factors, local resistance patterns, and emerging evidence. Prescription decisions must be made by a qualified healthcare professional. Patients should never self-medicate with meropenem or any prescription antibiotic. If you have questions about your health or medication, consult your physician, pharmacist, or another licensed provider. If you are experiencing a medical emergency, seek immediate medical attention.





