
Dicloxacillin Uses and Side Effects 10 Powerful Facts, Dosage & Safety Warnings
Dicloxacillin Uses and Side Effects: 9 Important Facts About Safe Antibiotic Use
What if a single antibiotic capsule — small enough to fit on your fingertip — could mean the difference between a rapidly resolving skin infection and a life-threatening case of sepsis or infective endocarditis? That is the clinical reality of dicloxacillin, a penicillinase-resistant penicillin that has quietly saved countless patients from dangerous staphylococcal infections since its approval in the 1960s.
But here is the twist that catches even experienced clinicians off guard: dicloxacillin is not a broad-spectrum antibiotic. It is a precision tool designed for one major job — killing penicillinase-producing Staphylococcus aureus. Used correctly, it clears skin and soft tissue infections while sparing the microbiome. Used incorrectly, it fails, breeds resistance, and exposes patients to avoidable adverse effects.
Different antibiotics work against different bacteria, reach different tissues, have different pharmacological properties, and carry different risks. The appropriate choice depends on the suspected or confirmed organism, site and severity of infection, local resistance patterns, allergies, kidney and liver function, drug interactions, and patient-specific considerations. Dicloxacillin occupies a narrow but vital niche in this landscape — and understanding it fully is essential for anyone prescribing, dispensing, or studying antibiotics.
What you are about to read will challenge the way you think about this drug. We will explore 9 powerful facts about dicloxacillin uses and side Effects — from its FDA-approved indications and precise dosing strategies to its spectrum of activity, resistance challenges, and the latest evidence from clinical studies. Whether you are a medical student preparing for clinical rounds, a practicing clinician refining antimicrobial stewardship, or a pharmacist ensuring safe dispensing, the clinically important details in this article will strengthen your understanding of this remarkable antibiotic. Stay with us — because the details that make dicloxacillin truly powerful are revealed progressively.
A sobering clinical reality first: adverse drug reactions account for a significant proportion of hospital admissions, and beta-lactam antibiotics like dicloxacillin are among the most commonly implicated drug classes. Understanding the full safety profile is not optional — it is essential. For a suspenseful, evidence-based look at this hidden crisis, explore Shocking Adverse Drug Reaction Facts before you prescribe another beta-lactam.
Key Facts Table: Dicloxacillin at a Glance
The following table summarizes the most clinically important facts about dicloxacillin. This is not a substitute for full prescribing information, but it provides a rapid reference for healthcare professionals and students.
| Parameter | Details |
|---|---|
| Generic Name | Dicloxacillin sodium |
| Common Brand Names | Dynapen, Dycill, Pathocil (historical); generic capsules widely available |
| Drug Class | Penicillinase-resistant penicillin (isoxazolyl penicillin) |
| Therapeutic Class | Antibacterial (beta-lactam antibiotic) |
| Pharmacologic Class | Cell wall synthesis inhibitor |
| ATC Code | J01CF01 |
| Available Strengths | Capsules: 250 mg and 500 mg |
| Dosage Forms | Oral capsules |
| Route(s) of Administration | Oral only |
| FDA Status | FDA-approved (prescription only) |
| Primary Clinical Uses | Skin and skin structure infections caused by penicillinase-producing staphylococci |
| Bioavailability | Rapid but incomplete; food delays absorption |
| Protein Binding | 97.9% ± 0.6% (primarily albumin) |
| Volume of Distribution | Distributed to pleural, bile, and amniotic fluids; negligible CNS penetration |
| Half-Life | Approximately 0.7 hours |
| Metabolism | Partial hepatic inactivation; primarily excreted unchanged |
| Major Route of Elimination | Renal (glomerular filtration and active tubular secretion) |
| Renal/Hepatic Considerations | Not dialyzable; caution in severe renal or hepatic impairment |
| Major Contraindications | Hypersensitivity to penicillins; previous severe allergic reaction |
| Important Adverse Effects | GI upset, rash, hypersensitivity, esophagitis, C. difficile-associated diarrhea |
This table is a snapshot. Every parameter in it will be expanded in the dedicated sections below, but we will not repeat the full explanations unnecessarily.
FDA-Approved Uses
The U.S. Food and Drug Administration (FDA) has granted dicloxacillin approval for a specific and narrow set of clinical indications. Understanding these approved uses is essential for appropriate prescribing and antimicrobial stewardship. This section details what is dicloxacillin used for from an FDA standpoint, along with pathogen and dosing details.
- Skin and Skin Structure Infections Caused by Penicillinase-Producing Staphylococci:
Dicloxacillin is indicated for the treatment of skin infections caused by susceptible staphylococcal species. This includes conditions such as impetigo, cellulitis, and other pyodermas where penicillinase-producing S. aureus is the confirmed or suspected pathogen. Dosage: Adults — 250–500 mg orally every 6 hours for 10 days, depending on the nature and severity of the infection. - Infections Caused by Penicillinase-Producing Staphylococci (General):
Cultures and susceptibility tests should be performed initially to determine the causative organisms and their sensitivity to dicloxacillin. The drug may also be used to initiate therapy in suspected cases of resistant staphylococcal infections prior to the availability of laboratory test results.
Guideline-Supported Uses: The Infectious Diseases Society of America (IDSA) recommends dicloxacillin as a first-line oral agent for non-purulent cellulitis without MRSA risk factors. The 2014 IDSA skin and soft tissue infection guidelines suggest dicloxacillin 500 mg four times daily or cephalexin 500 mg four times daily for 5–7 days for mild, non-purulent cellulitis. The World Health Organization (WHO) also lists dicloxacillin as a first-choice antibiotic for mild skin and soft tissue infections. For a broader comparison of antibiotic options, explore What Is Cephalexin Used For? 8 Answers You Need to Know to understand how cephalexin compares with dicloxacillin for skin infections.
Off-Label or Investigational Uses: Dicloxacillin has been studied in diabetic foot infections caused by methicillin-susceptible S. aureus, though it is not FDA-approved for this specific indication. Any use outside the FDA-approved indication should be based on clinical judgment, culture and susceptibility data, and guideline recommendations — and should not be classified as FDA-approved.
Dosage Table
The table below provides a concise summary of typical dosing for common indications. Doses may vary based on renal and hepatic function, severity, and susceptibility data. This table covers dicloxacillin dosage for adult and pediatric patients.
| Patient/Condition | Recommended Dose | Frequency | Duration | Important Considerations |
|---|---|---|---|---|
| Adults — Mild Staphylococcal Infection | 125 mg | Every 6 hours | 7–10 days | Lowest effective dose; confirm susceptibility. |
| Adults — Moderate Staphylococcal Infection | 250 mg | Every 6 hours | 7–10 days | Adjust based on clinical response. |
| Adults — Severe Staphylococcal Infection | 500 mg | Every 6 hours | 10 days or more | Higher doses may be needed; monitor closely. |
| Adults — Non-Purulent Cellulitis (IDSA) | 500 mg | Four times daily | 5–7 days | First-line oral option for MSSA when MRSA not suspected. |
| Children ≥ 40 kg | Same as adult | Every 6 hours | Individualize | Do not exceed adult dose. |
| Children < 40 kg | 12.5–50 mg/kg/day | Divided every 6 hours | Individualize | Dose depends on severity. |
| Neonates | Not established | — | — | Not recommended due to limited experience. |
| Elderly Patients | Start low | Every 6 hours | Individualize | Consider renal/hepatic function. |
Important: The dose and duration of dicloxacillin depend on diagnosis, age, weight, renal and hepatic function, severity and site of infection, and clinical response. Never prescribe dicloxacillin without confirming or strongly suspecting a susceptible staphylococcal infection. Inappropriate use fuels resistance and exposes patients to unnecessary risk.
Mechanism of Action
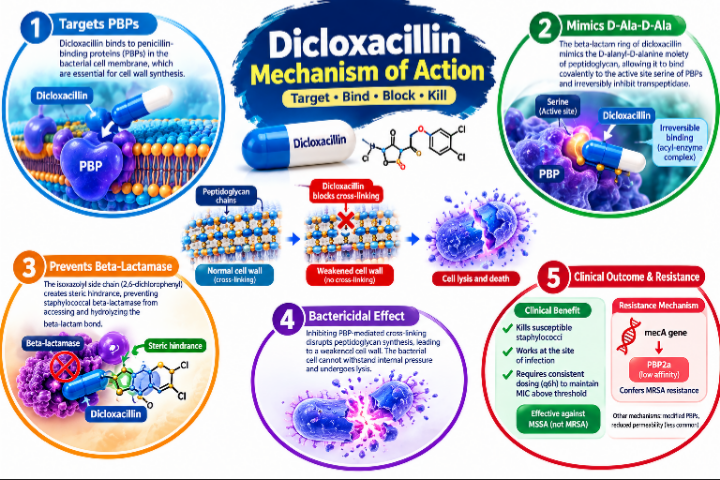
Dicloxacillin exerts its bactericidal effect through a well-characterized molecular mechanism that distinguishes it from many other antibiotic classes. Understanding this mechanism is fundamental to appreciating both its clinical utility and its limitations.
Primary Molecular Target: Dicloxacillin, like all beta-lactam antibiotics, targets penicillin-binding proteins (PBPs) — a group of enzymes embedded in the bacterial cytoplasmic membrane that are essential for cell wall synthesis. Specifically, dicloxacillin binds to and inhibits PBPs involved in the cross-linking of peptidoglycan chains.
Binding and Interaction: The beta-lactam ring of dicloxacillin is structurally analogous to the terminal D-alanyl-D-alanine moiety of peptidoglycan precursors. This molecular mimicry allows dicloxacillin to bind covalently to the active site serine residue of PBPs, forming a stable acyl-enzyme complex that irreversibly inhibits transpeptidase activity. The isoxazolyl side chain — the 2,6-dichlorophenyl group attached to the isoxazole ring — creates steric hindrance that prevents staphylococcal beta-lactamase from accessing and hydrolyzing the beta-lactam bond.
Cellular Pathway Affected: By inhibiting PBP-mediated cross-linking, dicloxacillin disrupts the final stages of peptidoglycan synthesis. This leads to a weakened cell wall that cannot withstand the internal osmotic pressure of the bacterial cytoplasm. The result is bacterial cell lysis and death — a bactericidal effect.
Physiologic and Clinical Consequences: The clinical therapeutic effect of dicloxacillin — bacterial killing at the site of infection — depends on achieving adequate free drug concentrations at the target tissue for a sufficient duration. This is why dosing regimens are designed to maintain serum and tissue concentrations above the minimum inhibitory concentration (MIC) for the infecting organism throughout the dosing interval.
Resistance Mechanisms: Resistance to dicloxacillin occurs primarily through the acquisition of the mecA gene, which encodes an alternative penicillin-binding protein (PBP2a) with low affinity for all beta-lactam antibiotics. This mechanism confers methicillin resistance and renders dicloxacillin ineffective against MRSA. Other resistance mechanisms include modifications of endogenous PBPs and reduced outer membrane permeability, though these are less common in S. aureus.
What Is Dicloxacillin?
Dicloxacillin is a semisynthetic antibiotic belonging to the isoxazolyl penicillin series, a subgroup of the penicillinase-resistant penicillins. It is a penicillinase-resistant, acid-resistant penicillin suitable for oral administration. Chemically, it is monosodium (2S,5R,6R)-6-[3-(2,6-dichlorophenyl)-5-methyl-4-isoxazolecarboxamido]-3,3-dimethyl-7-oxo-4-thia-1-azabicyclo[3.2.0]heptane-2-carboxylate monohydrate.
Drug Class and Pharmacologic Classification: The generic name is dicloxacillin sodium. It belongs to the penicillinase-resistant penicillin (isoxazolyl penicillin) drug class, with pharmacologic classification as a cell wall synthesis inhibitor. Therapeutically, it is an antibacterial agent effective against penicillinase-producing gram-positive bacteria.
Therapeutic Role: Dicloxacillin is positioned as an oral antibiotic for skin and soft tissue infections caused by methicillin-susceptible Staphylococcus aureus (MSSA). Its role is particularly important in outpatient settings where intravenous therapy is not required. It is one of the few oral antibiotics that reliably covers penicillinase-producing staphylococci, making it a valuable tool in the antimicrobial armamentarium.
Formulations, Strengths, and Routes: Dicloxacillin is available as oral capsules containing dicloxacillin sodium equivalent to 250 mg or 500 mg of dicloxacillin. The capsules also contain inactive ingredients including magnesium stearate, gelatin, and various coloring agents. The route of administration is oral only.
Differences from Closely Related Medicines: Dicloxacillin is closely related to other isoxazolyl penicillins such as cloxacillin, flucloxacillin, and oxacillin. Compared to oxacillin, dicloxacillin achieves higher serum concentrations after oral administration. Compared to flucloxacillin — which is more commonly used in Europe and Australia — dicloxacillin is the primary oral anti-staphylococcal penicillin available in the United States. For a detailed comparison of flucloxacillin, you can explore our Flucloxacillin (Floxapen) uses and side effects guide. Compared to cephalexin — a first-generation cephalosporin — dicloxacillin has a narrower spectrum and is specifically optimized for MSSA coverage. Both agents are considered first-line options for non-purulent cellulitis, but dicloxacillin has no activity against gram-negative organisms, whereas cephalexin provides some coverage against certain gram-negative bacteria such as E. coli and Klebsiella species.
Pharmacokinetics & Pharmacodynamics Key Table
The following table summarizes the key pharmacokinetic (PK) and pharmacodynamic (PD) properties that inform the clinical use of dicloxacillin.
| Parameter | Clinically Relevant Details |
|---|---|
| Absorption | Rapid but incomplete after oral administration; peak in 1–1.5 hours. |
| Bioavailability | Variable; food delays absorption. |
| Time to Peak Concentration | 1–1.5 hours fasting; delayed with food. |
| Protein Binding | 97.9% ± 0.6%, primarily albumin. |
| Volume of Distribution | Distributed to pleural, bile, and amniotic fluids; negligible CNS penetration. |
| Tissue Penetration | Therapeutic in pleural, bile, and amniotic fluids; poor in CSF and aqueous humor. |
| Blood-Brain Barrier Penetration | Insignificant; not for CNS infections. |
| Placental Transfer | Found in amniotic fluid, suggesting transfer. |
| Half-Life | Approximately 0.7 hours. |
| Metabolism | Partial hepatic inactivation; primarily excreted unchanged. |
| Active Metabolites | Not clinically significant. |
| Enzyme Involvement | Inducer of CYP3A4, CYP2C19, and CYP2C9. |
| Elimination | Primarily renal (glomerular filtration and active tubular secretion). |
| Renal Clearance | Major pathway; not significantly dialyzable. |
| Fecal/Biliary Elimination | Minor pathway. |
| Pharmacodynamic Target | Penicillin-binding proteins (PBPs). |
| Mechanism | Inhibition of bacterial cell wall synthesis. |
| Concentration/Time-Dependent Activity | Time-dependent bactericidal activity. |
| PK/PD Index | Time above MIC (T > MIC). |
This table is a quick reference. The following sections explain the most important details without unnecessary repetition.
Half-Life
The elimination half-life of dicloxacillin is approximately 0.7 hours — one of the shortest among the penicillinase-resistant penicillins. This short half-life reflects the drug’s rapid renal clearance through glomerular filtration and active tubular secretion.
Clinical Significance of the Short Half-Life: The half-life of dicloxacillin directly influences its dosing frequency. Because the drug is eliminated from the body relatively quickly, it must be administered every 6 hours to maintain serum concentrations above the minimum inhibitory concentration (MIC) for susceptible organisms. Missing doses or extending the dosing interval can lead to subtherapeutic drug levels and treatment failure.
Factors That Alter Half-Life: Renal impairment can prolong the half-life of dicloxacillin because the kidneys are the primary route of elimination. However, the drug is not significantly removed by hemodialysis or peritoneal dialysis, so dose adjustments in dialysis patients are based on clinical response rather than a predictable pharmacokinetic alteration. Hepatic impairment may also affect the non-renal elimination pathway, though the clinical significance is less well-established.
Why Half-Life Matters Clinically: A short half-life means that consistent dosing intervals are essential for therapeutic success. Patients should be counseled on the importance of taking dicloxacillin every 6 hours, ideally at evenly spaced intervals throughout the day. The short half-life also explains why dicloxacillin is not suitable for once-daily or twice-daily dosing regimens.
Metabolism
Dicloxacillin undergoes partial hepatic metabolism, but the majority of the drug is excreted unchanged in the urine. The hepatic component involves inactivation of the drug, likely through hydrolysis of the beta-lactam ring, though specific metabolic pathways and enzymes have not been fully characterized in the published literature.
Enzyme Interactions: More clinically important than the metabolism of dicloxacillin itself is its effect on hepatic enzymes. Dicloxacillin is a clinically relevant inducer of cytochrome P450 enzymes, specifically CYP3A4, CYP2C19, and CYP2C9. This enzyme induction can reduce the plasma concentrations and therapeutic efficacy of co-administered drugs that are metabolized by these enzymes.
Clinical Implications: The enzyme-inducing properties of dicloxacillin mean that clinicians must be vigilant about potential drug interactions when prescribing this antibiotic. Drugs with narrow therapeutic windows that are metabolized by CYP3A4, CYP2C19, or CYP2C9 — such as warfarin, voriconazole, and certain immunosuppressants — may require dose adjustments or additional monitoring during dicloxacillin therapy.
Renal and Hepatic Impairment: In patients with significant renal impairment, the non-renal elimination pathways become relatively more important, but dicloxacillin is still primarily dependent on renal clearance. Hepatic impairment may theoretically reduce the metabolic component of elimination, but the clinical significance is not well-defined. Clinicians should monitor patients with combined renal and hepatic impairment closely.
Bioavailability & Protein Binding
Oral Bioavailability: Dicloxacillin is acid-resistant and suitable for oral administration, but its absorption is rapid yet incomplete. After oral administration, peak blood levels are achieved in 1 to 1.5 hours. In one study, after ingestion of a single 500 mg oral dose, peak serum concentrations ranged from 10 to 17 mcg/mL.
Factors Affecting Absorption: The most important factor affecting dicloxacillin absorption is food. Oral absorption is delayed when the drug is administered after meals. This means that taking dicloxacillin with food can reduce peak serum concentrations and potentially compromise therapeutic efficacy, particularly in the early phase of treatment.
Protein Binding: Once absorbed, dicloxacillin is extensively bound to serum proteins, primarily albumin, at a rate of 97.9% ± 0.6%. This high degree of protein binding has several clinical implications.
Clinical Significance of Protein Binding: The high protein binding of dicloxacillin means that only a small fraction of the total drug in the bloodstream is pharmacologically active. The free (unbound) drug is the fraction that can diffuse into tissues, bind to PBPs, and exert antibacterial activity. However, the high protein binding also means that dicloxacillin has a relatively small volume of distribution for free drug, which may limit its penetration into certain tissue compartments. Despite the high protein binding, dicloxacillin achieves therapeutic concentrations in several body fluids, including pleural fluid, bile, and amniotic fluid. However, it does not achieve significant concentrations in cerebrospinal fluid or aqueous humor, making it unsuitable for CNS infections or ocular infections. For a deeper dive into this concept, refer to our detailed guide on plasma protein binding.
Spectrum of Activity
Dicloxacillin has a relatively narrow spectrum of activity compared to broader-spectrum antibiotics like amoxicillin or cephalexin. Its spectrum is specifically optimized for gram-positive organisms, particularly penicillinase-producing staphylococci.
Gram-Positive Activity: Dicloxacillin is active against most strains of Staphylococcus aureus, including both penicillinase-producing and non-penicillinase-producing strains. It is also active against other gram-positive cocci, though its activity against streptococci is generally inferior to that of penicillin G. The drug is not active against Enterococcus species, which are intrinsically resistant to all penicillinase-resistant penicillins.
Gram-Negative Activity: Dicloxacillin has essentially no clinically useful activity against gram-negative bacteria. This is a critical limitation of the drug’s spectrum and explains why it should not be used for infections where gram-negative organisms are suspected or confirmed.
Anaerobic Activity: Dicloxacillin has limited activity against anaerobic bacteria. It is not a reliable agent for anaerobic infections, and alternative antibiotics should be selected when anaerobic coverage is required.
Important Susceptible Pathogens: Staphylococcus aureus (penicillinase-producing and non-penicillinase-producing strains), Staphylococcus epidermidis (some strains), Streptococcus pyogenes (Group A Streptococcus) — though penicillin G is superior.
Important Intrinsic Resistance: Methicillin-resistant Staphylococcus aureus (MRSA), Enterococcus species, gram-negative bacteria, anaerobic bacteria.
Clinical Significance of Susceptibility Testing: Because dicloxacillin’s spectrum is narrow and resistance patterns can vary by geographic region and healthcare setting, susceptibility testing is essential when the drug is being considered for treatment. The FDA label explicitly states that cultures and susceptibility tests should be performed initially to determine the causative organisms and their sensitivity to the drug. Empiric use should be reserved for situations where a susceptible staphylococcal infection is strongly suspected based on clinical presentation and local epidemiology. For a broader perspective on antibiotic selection, understanding what amoxicillin covers provides useful comparative context.
Pharmacodynamics
The pharmacodynamics of dicloxacillin — how the drug exerts its effects on bacteria — provides the scientific rationale for dosing strategies and explains why certain dosage regimens are more effective than others.
Drug-Target Interaction: Dicloxacillin’s primary pharmacodynamic action is inhibition of penicillin-binding proteins (PBPs), leading to disruption of peptidoglycan cross-linking and bacterial cell lysis. The drug exhibits bactericidal activity — it kills bacteria rather than merely inhibiting their growth — which is a desirable property for treating serious infections.
Concentration-Response Relationship and Time-Dependent Killing: Beta-lactam antibiotics, including dicloxacillin, exhibit time-dependent killing. This means that the extent of bacterial killing is primarily determined by the duration of time that the free drug concentration remains above the minimum inhibitory concentration (MIC) for the infecting organism, rather than by peak concentration. The PK/PD index that best correlates with efficacy for beta-lactams is the percentage of the dosing interval during which the free drug concentration exceeds the MIC (%T > MIC).
Therapeutic Window: The therapeutic window for dicloxacillin — the range between effective and toxic concentrations — is relatively favorable in patients with normal renal function. However, the drug’s narrow spectrum and the potential for hypersensitivity reactions require careful patient selection.
Post-Antibiotic Effect: Dicloxacillin demonstrates a modest post-antibiotic effect against gram-positive organisms, meaning that bacterial growth remains suppressed for a short period after drug concentrations fall below the MIC. However, this effect is not sufficiently prolonged to justify less frequent dosing.
Resistance Suppression: Maintaining adequate drug concentrations throughout the dosing interval not only maximizes bacterial killing but also suppresses the emergence of resistant mutants. Sub-therapeutic drug concentrations — which can occur when patients miss doses or take dicloxacillin with food (which delays absorption) — can expose bacteria to sub-inhibitory antibiotic concentrations, creating selective pressure for resistant strains. This is a critical consideration for antimicrobial stewardship.
Contraindications
Absolute Contraindications: Dicloxacillin is contraindicated in patients with a known history of serious hypersensitivity reactions to any penicillin or beta-lactam antibiotic. This includes anaphylaxis, angioedema, and severe urticarial reactions. A history of Stevens-Johnson syndrome, toxic epidermal necrolysis, or other severe cutaneous adverse reactions to penicillins is also an absolute contraindication.
Major Hypersensitivity Contraindications: Patients with a history of immediate-type hypersensitivity reactions (occurring within 1 hour of drug administration) to penicillins should not receive dicloxacillin. This includes patients who have experienced bronchospasm, laryngeal edema, or hypotension following penicillin administration.
Formulation-Specific Contraindications: Dicloxacillin capsules contain inactive ingredients including gelatin, magnesium stearate, and various coloring agents. Patients with known hypersensitivity to any of these excipients should not receive the specific formulation containing the offending agent.
What Is Not a Contraindication: A history of mild, non-urticarial rash occurring days after penicillin administration is not necessarily an absolute contraindication, but it should prompt careful evaluation and consideration of alternative antibiotics. Similarly, a family history of penicillin allergy without a personal history of reaction does not constitute a contraindication.
Warnings & Precautions
- Hypersensitivity Reactions: Serious and occasionally fatal hypersensitivity reactions, including anaphylaxis, have been reported with penicillins. Before initiating dicloxacillin therapy, clinicians should inquire about previous hypersensitivity reactions to penicillins, cephalosporins, and other allergens. If an allergic reaction occurs, the drug should be discontinued immediately and appropriate emergency treatment instituted.
- Renal Impairment: Dicloxacillin is primarily eliminated by the kidneys. In patients with significant renal impairment, drug accumulation may occur, potentially increasing the risk of adverse effects. While specific dose adjustment guidelines are not well-established, clinicians should monitor renal function and consider alternative antibiotics in patients with severe renal impairment.
- Hepatic Impairment: Dicloxacillin undergoes partial hepatic metabolism. The clinical significance of hepatic impairment on dicloxacillin pharmacokinetics is not well-defined, but caution is warranted in patients with severe liver disease. Monitoring of liver function may be appropriate in patients with pre-existing hepatic impairment.
- Pregnancy: Human experience with penicillins during pregnancy has not shown any positive evidence of adverse effects on the fetus. However, there are no adequate and well-controlled studies in pregnant women showing conclusively that harmful effects can be excluded. Dicloxacillin should be used during pregnancy only if clearly needed.
- Breastfeeding: Penicillins are excreted in human breast milk. Caution should be exercised when dicloxacillin is administered to a nursing woman. There is a potential risk of effects on the infant’s oral and intestinal flora, and small quantities in breast milk may increase the risk of sensitization.
- Esophageal Irritation: Rare reports of esophageal burning, esophagitis, and esophageal ulceration have been received during postmarketing surveillance, particularly after ingestion of dicloxacillin capsules with an insufficient quantity of water and/or before going to bed. To minimize this risk, dicloxacillin should be taken with at least 4 fluid ounces (120 mL) of water, and patients should remain upright for at least 30 minutes after taking the medication.
- Clostridioides difficile-Associated Diarrhea: Antibacterial agents, including dicloxacillin, can cause Clostridioides difficile-associated diarrhea (CDAD). This condition can range in severity from mild diarrhea to fatal colitis. It is important to consider CDAD in patients who present with diarrhea following antibiotic use. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued.
- Pediatric Use: Because of incompletely developed renal function in newborns, penicillinase-resistant penicillins may not be completely excreted, potentially resulting in abnormally high blood levels. Experience in the neonatal period is limited, and a dose for newborns is not recommended.
- Geriatric Use: Clinical studies of dicloxacillin have not included sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for elderly patients should be cautious, starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function.
Side Effects
Understanding the side effect profile of dicloxacillin is essential for patient counseling and clinical monitoring. Adverse effects are broadly categorized by frequency, and distinguishing between common, bothersome side effects and serious adverse reactions is clinically important.
Common Side Effects:
- Nausea, vomiting, and abdominal discomfort — the most common complaints.
- Diarrhea or loose stools.
- Rash and urticaria.
- Gastrointestinal upset that may be reduced by taking the medication with food.
Less Common Side Effects:
- Hematologic effects: eosinophilia, leukopenia, neutropenia, and thrombocytopenia.
- Hepatic effects: transient elevations in serum transaminases (AST, ALT) and alkaline phosphatase.
- Renal effects: interstitial nephritis, though rare with dicloxacillin.
- Neurologic effects: confusion, seizures, and hallucinations, particularly in patients with renal impairment receiving high doses.
- Superinfection: overgrowth of non-susceptible organisms, including Candida species.
Distinguishing Side Effects from Adverse Reactions: It is important for clinicians to distinguish between side effects (predictable, often dose-related, and generally manageable) and adverse reactions (unexpected, potentially serious, and requiring medical intervention). Diarrhea associated with dicloxacillin is typically a side effect related to alterations in gut flora. However, if diarrhea is severe, persistent, or accompanied by fever, abdominal pain, or blood in the stool, it may indicate Clostridioides difficile infection — a serious adverse reaction requiring immediate medical evaluation.
Adverse Effects
While the common side effects of dicloxacillin are generally mild and self-limiting, the drug carries a risk of serious adverse effects that all prescribers must recognize and monitor for.
- Serious Hypersensitivity Reactions: Anaphylaxis is the most feared adverse reaction to dicloxacillin, though it occurs in fewer than 1 in 1,000 patients. Symptoms include urticaria, angioedema, bronchospasm, hypotension, and cardiovascular collapse. Anaphylaxis typically occurs within minutes to hours of drug administration and requires immediate treatment with epinephrine, airway management, and supportive care.
- Severe Dermatologic Reactions: Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN) are rare but potentially fatal mucocutaneous reactions that have been reported with penicillins. These reactions are characterized by widespread erythema, bullae formation, and epidermal detachment, often involving the mucous membranes. Early recognition and immediate drug discontinuation are critical.
- Clostridioides difficile-Associated Diarrhea (CDAD): CDAD is a significant adverse effect of all antibacterial agents, including dicloxacillin. Symptoms range from mild watery diarrhea to fulminant colitis with toxic megacolon, perforation, and death. Risk factors include advanced age, hospitalization, prolonged antibiotic courses, and concurrent use of proton pump inhibitors.
- Neurologic Effects: High doses of penicillins, particularly in patients with renal impairment, can cause neurotoxicity. This may manifest as confusion, myoclonus, seizures, or hallucinations. The risk is increased when drug accumulation occurs due to impaired renal clearance.
- Hematologic Effects: Penicillins can cause a range of hematologic abnormalities, including eosinophilia, leukopenia, neutropenia, thrombocytopenia, and rarely, hemolytic anemia. These effects are generally reversible upon discontinuation of the drug.
- Hepatic and Renal Effects: Transient elevations in liver enzymes are common and usually resolve without intervention. Rare cases of cholestatic hepatitis have been reported. Interstitial nephritis is a rare but serious renal adverse effect that can occur with any penicillin.
- When to Seek Medical Attention: Patients should be instructed to seek immediate medical attention if they experience any of the following: severe or persistent diarrhea, bloody stools, rash or hives, swelling of the face or throat, difficulty breathing, fever, jaundice, dark urine, or seizures. Prompt recognition and management of these serious adverse reactions can be life-saving.
Drug Interactions
The following table summarizes clinically meaningful drug interactions with dicloxacillin. Theoretical interactions of little clinical relevance have been omitted.
| Interacting Medicine/Class | Potential Interaction | Clinical Significance | Management Consideration |
|---|---|---|---|
| Warfarin | Dicloxacillin may reduce the anticoagulant response to warfarin, possibly through hepatic enzyme induction. | Reduced anticoagulant effect, increased risk of thromboembolism. | Monitor prothrombin time/INR closely; adjust warfarin dose as needed. |
| Tetracyclines | Bacteriostatic tetracyclines may antagonize the bactericidal effect of penicillins. | Potential reduced efficacy. | Avoid concurrent use when possible. |
| Probenecid | Probenecid increases and prolongs serum penicillin levels by inhibiting renal tubular secretion. | Increased penicillin levels; potential for increased toxicity. | Used therapeutically in some contexts; monitor for adverse effects. |
| Aminoglycosides | Penicillins can physically/chemically inactivate aminoglycosides in vitro. | Reduced aminoglycoside efficacy. | Administer separately; avoid in vitro mixing. |
| Voriconazole | Dicloxacillin induces CYP2C19 and CYP3A4, reducing voriconazole concentrations. | Reduced antifungal efficacy. | Consider alternative antifungal or monitor voriconazole levels. |
| CYP3A4 Substrates | Dicloxacillin is a clinically relevant CYP3A4 inducer. | Reduced concentrations of CYP3A4 substrates. | Monitor for reduced efficacy of co-administered drugs. |
| Direct Oral Anticoagulants | Dicloxacillin induces P-glycoprotein and CYP3A4. | Potential reduced anticoagulant effect. | Monitor for signs of thrombosis; consider alternative antibiotic. |
| Methotrexate | Penicillins may reduce renal clearance of methotrexate. | Increased methotrexate toxicity. | Monitor methotrexate levels and for toxicity. |
| Oral Contraceptives | Rare reports of reduced contraceptive efficacy with antibiotics. | Potential for unintended pregnancy. | Advise additional contraceptive precautions during therapy. |
Administration Table
Practical administration instructions are essential for patient education and nursing practice. The table below summarizes key administration factors.
| Administration Factor | Guidance |
|---|---|
| Route | Oral only. |
| With Food/Without Food | Absorption is delayed when taken with food; administer on an empty stomach when possible. |
| Timing | Every 6 hours for optimal therapeutic levels. |
| Tablet/Capsule Instructions | Take with at least 4 fluid ounces (120 mL) of water. |
| Liquid Formulation | Not available in the United States. |
| IV Administration | Not applicable (oral formulation only). |
| Missed Dose | Take as soon as remembered; if close to next dose, skip missed dose; do not double dose. |
| Storage | Store at controlled room temperature (20°C–25°C); keep in original container. |
| Special Administration Instructions | Remain upright for at least 30 minutes after taking to reduce esophageal irritation risk. Complete the full prescribed course even if symptoms improve. |
Pharmacokinetics
This section consolidates the clinically relevant pharmacokinetic properties of dicloxacillin in a professional overview. Detailed explanations of half-life, metabolism, bioavailability, and protein binding are provided in their respective dedicated sections above and are not repeated here.
Absorption and Bioavailability: Dicloxacillin is rapidly absorbed after oral administration, with peak serum concentrations achieved in 1 to 1.5 hours. However, absorption is incomplete, and the presence of food in the stomach delays absorption. After a single 500 mg oral dose, peak serum concentrations range from 10 to 17 mcg/mL.
Distribution: Once absorbed, dicloxacillin is extensively bound to serum proteins, primarily albumin (97.9% ± 0.6%). The drug is distributed to pleural fluid, bile, and amniotic fluid, where therapeutic concentrations are achieved. However, it does not achieve significant concentrations in cerebrospinal fluid or aqueous humor, making it unsuitable for infections in these compartments.
Metabolism and Elimination: Dicloxacillin undergoes partial hepatic inactivation, but the majority of the drug is excreted unchanged in the urine via glomerular filtration and active tubular secretion. The elimination half-life is approximately 0.7 hours. Non-renal elimination includes hepatic inactivation and biliary excretion. The drug is not significantly removed by hemodialysis or peritoneal dialysis.
Special Populations: In patients with severe renal impairment, the elimination half-life may be prolonged, but specific dose adjustment guidelines are not well-established. Caution and close monitoring are recommended. The clinical significance of hepatic impairment on dicloxacillin pharmacokinetics is not well-defined, but caution is warranted in severe liver disease. Newborns have incompletely developed renal function, which may lead to drug accumulation. Experience in neonates is limited, and a dose for newborns is not recommended. Elderly patients may have decreased renal function, necessitating careful dose selection starting at the low end of the range.
Special Populations
Pregnancy: Human experience with penicillins during pregnancy has not shown any positive evidence of adverse effects on the fetus. However, there are no adequate and well-controlled studies in pregnant women showing conclusively that harmful effects can be excluded. Dicloxacillin should be used during pregnancy only if clearly needed.
Lactation: Penicillins are excreted in human breast milk at low levels. While harmful effects to breastfed infants are unlikely, there may be a risk of effects on the oral and intestinal flora, and small quantities in breast milk may increase the risk of sensitization. Caution should be exercised when prescribing dicloxacillin to breastfeeding women.
Pediatrics: Dicloxacillin is not recommended for use in neonates due to limited experience and the risk of drug accumulation secondary to incompletely developed renal function. For older children, dosing is based on body weight (12.5–50 mg/kg/day divided every 6 hours), not to exceed adult doses.
Older Adults: Clinical studies have not included sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. In general, dose selection should be cautious, starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy.
Renal Impairment: Dicloxacillin is primarily eliminated by the kidneys. In patients with significant renal impairment, drug accumulation may occur, increasing the risk of adverse effects, particularly neurotoxicity. While specific dose adjustment guidelines are not well-established, clinicians should monitor renal function and consider alternative antibiotics in patients with severe renal impairment.
Hepatic Impairment: The clinical significance of hepatic impairment on dicloxacillin pharmacokinetics is not well-defined. Caution is warranted in patients with severe liver disease, and monitoring of liver function may be appropriate.
Monitoring
- Clinical Response: Resolution of signs and symptoms of infection, including fever, erythema, swelling, and pain. Lack of clinical improvement within 48–72 hours may indicate the need for reassessment.
- Renal Function: Serum creatinine and blood urea nitrogen, particularly in patients with pre-existing renal impairment or those receiving concomitant nephrotoxic drugs.
- Hepatic Function: Liver enzymes (AST, ALT, alkaline phosphatase) in patients with hepatic impairment or those receiving long-term therapy.
- Microbiological Response: Culture and susceptibility results to guide therapy and confirm appropriate antibiotic selection.
- Adverse Reactions: Monitor for signs of hypersensitivity, gastrointestinal effects, and neurologic symptoms.
- Prothrombin Time/INR: In patients receiving concomitant warfarin therapy, monitor anticoagulant response closely.
- C. difficile Testing: In patients who develop diarrhea during or after therapy.
Clinical Perspective
From a clinical standpoint, dicloxacillin remains a valuable oral antibiotic for the treatment of skin and soft tissue infections caused by methicillin-susceptible Staphylococcus aureus. Its narrow spectrum and bactericidal activity make it an appropriate choice for non-purulent cellulitis without MRSA risk factors, consistent with IDSA guideline recommendations.
However, its clinical utility must be balanced against its limitations. The drug has no activity against MRSA, gram-negative organisms, or anaerobes. It must be dosed four times daily, and its absorption is significantly affected by food. These factors make dicloxacillin less convenient than some alternatives, such as cephalexin, which can be dosed twice daily and provides broader coverage.
When selecting dicloxacillin, clinicians should consider culture and susceptibility data, local resistance patterns, patient adherence, drug interactions, and patient-specific factors. Antimicrobial stewardship principles should guide the use of dicloxacillin. The drug should be reserved for confirmed or strongly suspected susceptible staphylococcal infections, and therapy should be de-escalated or discontinued as soon as clinically appropriate. For a comprehensive understanding of antibiotic stewardship in practice, exploring resources on safe antibiotic use and symptom management can provide valuable context.
Question. What is dicloxacillin used for?
Answer : Dicloxacillin is used to treat infections caused by penicillinase-producing staphylococci, particularly skin and soft tissue infections. It is FDA-approved for susceptible staphylococcal infections and is recommended by IDSA guidelines for non-purulent cellulitis.
Question. What is dicloxacillin 500 mg used for?
Answer : Dicloxacillin 500 mg is used for more severe staphylococcal infections, including moderate-to-severe skin and soft tissue infections. It is also the dose recommended by IDSA guidelines for non-purulent cellulitis without MRSA risk factors.
Question. How does dicloxacillin work?
Answer : Dicloxacillin works by inhibiting bacterial cell wall synthesis. It binds to penicillin-binding proteins (PBPs) in the bacterial cell membrane, preventing the cross-linking of peptidoglycan and causing bacterial cell death.
Question. How long does dicloxacillin take to work?
Answer : Clinical improvement is typically seen within 24–48 hours of starting therapy. However, the full course of treatment (usually 7–10 days) should be completed to ensure eradication of the infection and prevent recurrence.
Question. Can dicloxacillin treat a staph infection?
Answer : Yes, dicloxacillin is specifically designed to treat infections caused by penicillinase-producing Staphylococcus aureus. However, it is not effective against MRSA.
Question. What is the half-life of dicloxacillin?
Answer : The elimination half-life of dicloxacillin is approximately 0.7 hours. This short half-life requires dosing every 6 hours to maintain therapeutic drug levels.
Question. What are the common side effects of dicloxacillin 500 mg?
Answer : Common side effects include nausea, vomiting, diarrhea, abdominal discomfort, and rash. These are generally mild and resolve upon discontinuation of the drug.
Question. What are the serious adverse effects of dicloxacillin?
Answer : Serious adverse effects include anaphylaxis, severe cutaneous reactions (SJS, TEN), C. difficile-associated diarrhea, and neurotoxicity (especially in renal impairment).
Question. Is dicloxacillin FDA-approved?
Answer : Yes, dicloxacillin is FDA-approved for the treatment of infections caused by penicillinase-producing staphylococci that have demonstrated susceptibility to the drug.
Question. What infections does dicloxacillin treat?
Answer : Dicloxacillin treats skin and soft tissue infections caused by susceptible staphylococci, including cellulitis and impetigo. It is not effective against MRSA, gram-negative bacteria, or anaerobes.
Question. Can dicloxacillin be used during pregnancy?
Answer : Human experience with penicillins during pregnancy has not shown positive evidence of adverse fetal effects. However, dicloxacillin should be used during pregnancy only if clearly needed, as there are no adequate well-controlled studies.
Question. Can dicloxacillin be used while breastfeeding?
Answer : Penicillins are excreted in breast milk at low levels. Caution should be exercised when dicloxacillin is administered to a nursing woman due to potential effects on the infant’s flora and risk of sensitization.
Question. Does dicloxacillin interact with alcohol?
Answer : There is no specific interaction between dicloxacillin and alcohol, but alcohol may worsen gastrointestinal side effects. Patients should consult their healthcare provider about alcohol consumption during antibiotic therapy.
Question. What medicines interact with dicloxacillin?
Answer : Dicloxacillin interacts with warfarin (reduced anticoagulant effect), tetracyclines (antagonism), probenecid (increased penicillin levels), aminoglycosides (in vitro inactivation), and CYP3A4 substrates including voriconazole.
Question. What happens if a dose is missed?
Answer : Take the missed dose as soon as remembered. If it is almost time for the next dose, skip the missed dose and continue with the regular schedule. Do not double the dose.
Question. How should dicloxacillin be administered?
Answer : Dicloxacillin should be taken orally every 6 hours, with at least 4 fluid ounces of water, on an empty stomach when possible. Remain upright for at least 30 minutes after taking.
Question. Does renal impairment require dose adjustment?
Answer : Specific dose adjustment guidelines are not well-established, but caution is warranted in severe renal impairment due to potential drug accumulation and increased risk of neurotoxicity.
Question. Does hepatic impairment affect dicloxacillin use?
Answer : The clinical significance of hepatic impairment on dicloxacillin pharmacokinetics is not well-defined. Caution is warranted in severe liver disease.
Question. Is dicloxacillin safe for children?
Answer : Dicloxacillin can be used in children older than neonates at a dose of 12.5–50 mg/kg/day divided every 6 hours. It is not recommended for newborns due to limited experience.
Question. Is dicloxacillin appropriate for older adults?
Answer : Dicloxacillin can be used in older adults, but dose selection should be cautious, starting at the low end of the range due to age-related decreases in renal and hepatic function.
Question. What should clinicians monitor during dicloxacillin therapy?
Answer : Clinicians should monitor clinical response, renal and hepatic function, signs of adverse reactions, and prothrombin time/INR in patients on warfarin.
Question. What are alternatives to dicloxacillin?
Answer : Alternatives include cephalexin (for MSSA and broader gram-negative coverage), clindamycin (for penicillin-allergic patients), and trimethoprim-sulfamethoxazole or doxycycline (for MRSA coverage).
Question. What are the major contraindications to dicloxacillin?
Answer : Absolute contraindications include a history of serious hypersensitivity reactions to penicillins or beta-lactam antibiotics.
Question. How does resistance affect dicloxacillin use?
Answer : MRSA is resistant to dicloxacillin due to the mecA gene encoding PBP2a. Susceptibility testing is essential to confirm that the infecting organism is susceptible.
Question. How long does dicloxacillin treatment usually last?
Answer : Treatment duration is typically 7–10 days for most skin infections, but may be shorter (5–7 days) for uncomplicated cellulitis per IDSA guidelines.
Question. When should medical attention be sought during dicloxacillin therapy?
Answer : Seek immediate medical attention for signs of anaphylaxis (difficulty breathing, swelling of face/throat, hypotension), severe skin reactions, persistent diarrhea, or worsening infection despite antibiotic therapy.
5 Authentic Studies
Study 1
Citation: Stevens DL, Smith LG, Bruss JB, McConnell-Martin MA, Duvall SE, Todd WM, Hafkin B. Randomized comparison of linezolid (PNU-100766) versus oxacillin-dicloxacillin for treatment of complicated skin and soft tissue infections. Antimicrob Agents Chemother. 2000;44(12):3408-3413. doi:10.1128/AAC.44.12.3408-3413.2000
Study Type: Randomized, multicenter, open-label clinical trial.
Population: Patients with complicated skin and soft tissue infections.
Intervention/Exposure: Linezolid versus oxacillin-dicloxacillin.
Comparator: Oxacillin-dicloxacillin.
Main Outcome: Clinical cure rates.
Key Findings: Clinical success rates were similar between linezolid and oxacillin-dicloxacillin in the modified evaluable population. This study demonstrated that dicloxacillin (in combination with oxacillin) remains a viable comparator for newer agents in complicated skin infections.
Clinical Significance: The study supports the continued use of dicloxacillin-based regimens as effective therapy for complicated skin and soft tissue infections caused by susceptible organisms.
Important Limitation: The study was conducted before the widespread emergence of community-associated MRSA, which now limits the applicability of these findings in areas with high MRSA prevalence.
Study 2
Citation: Dillon HC Jr. Treatment of staphylococcal skin infections: A comparison of cephalexin and dicloxacillin. J Am Acad Dermatol. 1983;8(2):177-181. doi:10.1016/S0190-9622(83)70023-9
Study Type: Randomized controlled trial.
Population: Patients with staphylococcal skin and skin structure infections.
Intervention/Exposure: Cephalexin given twice daily versus dicloxacillin given four times daily.
Comparator: Dicloxacillin.
Main Outcome: Clinical and microbiological cure rates.
Key Findings: Cephalexin and dicloxacillin proved equally effective in treating staphylococcal skin infections. Only 2 of 64 strains were susceptible to penicillin G, confirming the prevalence of penicillinase-producing staphylococci.
Clinical Significance: This study provides evidence that dicloxacillin is as effective as cephalexin for staphylococcal skin infections, supporting its role as a first-line agent.
Important Limitation: The study was conducted in the 1980s and may not reflect current resistance patterns or patient populations.
Study 3
Citation: Wortman JM, Leegwater E, Wilms EB, Visser LG, van Nieuwkoop C. Pharmacokinetic drug–drug interactions with flucloxacillin and other isoxazolyl penicillins: A systematic literature review and practical guide. Br J Clin Pharmacol. 2026;92(6):1567-1583. doi:10.1002/bcp.70511
Study Type: Systematic literature review.
Population: Human studies reporting pharmacokinetic drug-drug interactions involving isoxazolyl penicillins.
Intervention/Exposure: Isoxazolyl penicillins (cloxacillin, dicloxacillin, flucloxacillin, oxacillin).
Comparator: Not applicable (systematic review).
Main Outcome: Characterization of drug-drug interactions and their clinical relevance.
Key Findings: The review identified 33 potential victim drugs across 51 articles. Most studies reported decreased exposure and/or efficacy of drugs during concomitant treatment with isoxazolyl penicillins. The most plausible mechanism appears to be induction of cytochrome P450 enzymes, UDP-glucuronosyltransferase enzymes, and P-glycoprotein.
Clinical Significance: This review provides a comprehensive, evidence-based resource for clinicians managing patients on dicloxacillin who are also taking other medications, particularly those with narrow therapeutic windows.
Important Limitation: The exact interaction mechanisms could not be fully elucidated due to the quality of study designs and heterogeneity in endpoints across included studies.
Study 4
Citation: Dijkmans AC, de Vries I, van Roon EN, et al. Microdialysis as a tool to determine the local tissue concentration of dicloxacillin in man. Br J Clin Pharmacol. 2018;84(4):779-788. doi:10.1111/bcp.13506
Study Type: Clinical pharmacokinetic study using microdialysis.
Population: Healthy adult volunteers.
Intervention/Exposure: Oral dicloxacillin administration with microdialysis sampling of muscle tissue.
Comparator: Plasma concentration versus tissue concentration.
Main Outcome: Tissue penetration of dicloxacillin.
Key Findings: The study found that dicloxacillin penetrates muscle tissue, and the ratio of AUC in tissue versus plasma showed no statistically significant difference. The high degree of protein binding (95–99%) was accounted for in the analysis.
Clinical Significance: This study provides direct evidence that dicloxacillin achieves therapeutic concentrations in soft tissue, supporting its use for skin and soft tissue infections.
Important Limitation: The study was conducted in healthy volunteers, and tissue penetration may differ in infected tissues or in patients with compromised circulation.
Study 5
Citation: Nielsen EI, Cars O, Friberg LE. Pharmacokinetic/pharmacodynamic (PK/PD) indices of antibiotics predicted by a semimechanistic PKPD model: a step toward model-based dose optimization. Antimicrob Agents Chemother. 2011;55(10):4619-4630. doi:10.1128/AAC.00182-11
Study Type: Pharmacokinetic/pharmacodynamic modeling study.
Population: In silico modeling based on published pharmacokinetic and pharmacodynamic data.
Intervention/Exposure: Evaluation of PK/PD indices for various antibiotics including penicillins.
Comparator: Different PK/PD indices (T > MIC, AUC/MIC, Cmax/MIC).
Main Outcome: Identification of the PK/PD index that best predicts efficacy.
Key Findings: For penicillins, including dicloxacillin, the time above MIC (T > MIC) is the PK/PD index that best correlates with bactericidal efficacy. This finding supports frequent dosing regimens to maintain drug concentrations above the MIC.
Clinical Significance: This study provides the pharmacodynamic rationale for the every-6-hour dosing schedule of dicloxacillin.
Important Limitation: The model is based on in vitro and animal data, and the findings may not fully translate to all clinical scenarios.
Authentic References
- Dicloxacillin Sodium Capsules USP. Prescribing Information. DailyMed, National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/
- Stevens DL, Bisno AL, Chambers HF, et al. Practice guidelines for the diagnosis and management of skin and soft tissue infections: 2014 update by the Infectious Diseases Society of America. Clin Infect Dis. 2014;59(2):e10-e52. doi:10.1093/cid/ciu444
- Liu C, Bayer A, Cosgrove SE, et al. Clinical practice guidelines by the Infectious Diseases Society of America for the treatment of methicillin-resistant Staphylococcus aureus infections in adults and children. Clin Infect Dis. 2011;52(3):e18-e55. doi:10.1093/cid/ciq146
- Stevens DL, Smith LG, Bruss JB, et al. Randomized comparison of linezolid versus oxacillin-dicloxacillin for treatment of complicated skin and soft tissue infections. Antimicrob Agents Chemother. 2000;44(12):3408-3413. doi:10.1128/AAC.44.12.3408-3413.2000
- Dillon HC Jr. Treatment of staphylococcal skin infections: A comparison of cephalexin and dicloxacillin. J Am Acad Dermatol. 1983;8(2):177-181. doi:10.1016/S0190-9622(83)70023-9
- Wortman JM, Leegwater E, Wilms EB, Visser LG, van Nieuwkoop C. Pharmacokinetic drug–drug interactions with flucloxacillin and other isoxazolyl penicillins: A systematic literature review and practical guide. Br J Clin Pharmacol. 2026;92(6):1567-1583. doi:10.1002/bcp.70511
- Dijkmans AC, de Vries I, van Roon EN, et al. Microdialysis as a tool to determine the local tissue concentration of dicloxacillin in man. Br J Clin Pharmacol. 2018;84(4):779-788. doi:10.1111/bcp.13506
- Nielsen EI, Cars O, Friberg LE. Pharmacokinetic/pharmacodynamic (PK/PD) indices of antibiotics predicted by a semimechanistic PKPD model: a step toward model-based dose optimization. Antimicrob Agents Chemother. 2011;55(10):4619-4630. doi:10.1128/AAC.00182-11
- Craig WA. Pharmacokinetic/pharmacodynamic parameters: rationale for antibacterial dosing of mice and men. Clin Infect Dis. 1998;26(1):1-10. doi:10.1086/516284
- Dicloxacillin — DrugBank. https://go.drugbank.com/drugs/DB00485
- Dicloxacillin — StatPearls. National Library of Medicine. Updated 2024.
- WHO Model List of Essential Medicines. World Health Organization. https://www.who.int/
- CDC Antimicrobial Resistance Threats. Centers for Disease Control and Prevention. https://www.cdc.gov/
- Dicloxacillin — LiverTox: Clinical and Research Information on Drug-Induced Liver Injury. National Institute of Diabetes and Digestive and Kidney Diseases.
- Dicloxacillin — ATC Code J01CF01. WHO Collaborating Centre for Drug Statistics Methodology.
- Dicloxacillin — Drug Interaction Report. Drugs.com.
- Dicloxacillin Use During Pregnancy and Breastfeeding — Drugs.com.
- Dicloxacillin — Pediatric Dosing. PedMed.
- Dicloxacillin — Renal Impairment Dosing. MedLibrary.
- Clostridioides difficile-Associated Diarrhea — FDA Prescribing Information. DailyMed.
Medical Information Disclaimer: The information provided in this article is for educational and informational purposes only and is intended for healthcare professionals, medical students, and informed general readers. It does not constitute medical advice, diagnosis, or treatment recommendations. Dicloxacillin is a prescription medication that should only be used under the supervision of a qualified healthcare provider. Treatment decisions, including dose selection, duration, and adjustments, depend on the patient’s diagnosis, age, renal and hepatic function, interacting medicines, susceptibility data where relevant, and clinician judgment. Readers should not use this information to self-medicate or to make clinical decisions without appropriate professional consultation. If you have a medical condition or are experiencing symptoms of infection, seek evaluation from a qualified healthcare professional. The authors and publishers of this article do not assume any liability for any adverse effects or consequences resulting from the use or misuse of the information provided herein.
For online earning ideas, freelancing, affiliate marketing, YouTube, Facebook monetization, and AI tips, visit ssthem.xyz for online earning and WhatsApp group links.





