
What Is Cephalexin Used For 8 Powerful Answers You Need to Know
What is cephalexin used for 9 Powerful That Crush Stubborn Infections and Restore Health Fast
Why does one antibiotic from the first generation of cephalosporins remain a first-line choice in modern medicine while newer, more powerful drugs have fallen to resistance or been relegated to last-resort status? The answer is not found in its age or a single clinical trial. It lives inside the drug’s remarkably targeted spectrum of activity, its near-perfect oral bioavailability, its minimal metabolic footprint, and the way it dismantles a bacterial cell wall with surgical precision. Cephalexin is not a broad-spectrum “shotgun” therapy designed to obliterate every bacterium in its path, yet it remains indispensable for specific, common infections where its focused power is exactly what the clinician needs.
A medical student may first encounter it as a “first-generation cephalosporin” and memorize its mechanism. A pharmacist may verify a dose and appreciate its clean interaction profile. A patient may search for cephalexin uses and side effects after receiving a prescription and wondering whether this “old” antibiotic is still the right choice. This article moves beyond a simple drug summary and provides a detailed, evidence-based exploration of cephalexin uses, covering cephalexin 500 mg uses, cephalexin dosage, cephalexin side effects, cephalexin for bacterial infections, and much more.
If you are a medical student, pharmacist, nurse, physician, researcher, or an informed patient seeking clarity, this guide is designed for you. But here is the first clinical caution: this article does not replace professional diagnosis or treatment, and cephalexin should never be used for self-medication. The details that matter most will unfold section by section.
Before we go deeper, remember that clinical pharmacology is not about memorizing isolated facts. It is about understanding why a drug works, when it works, when it should be avoided, and what can go wrong. In the following sections, we answer those questions with evidence.
One more thing: if you are comparing cephalosporins and wondering about the newer, more powerful sibling, ceftriaxone, you might be surprised by the clinical differences. For a suspenseful look at its uses and unique properties, explore Details about Ceftriaxone Sodium Uses . But keep your focus here first—the clinical stakes are high.
Key Facts Table: Cephalexin at a Glance
The following table summarizes the most clinically important facts about cephalexin. This is not a substitute for full prescribing information, but it provides a rapid reference for healthcare professionals and students.
| Parameter | Details |
|---|---|
| Generic Name | Cephalexin (also spelled cefalexin) |
| Common Brand Names | Keflex, Daxbia |
| Drug Class | Antibiotic (Cephalosporin, First Generation) |
| Therapeutic Class | Antibacterial |
| Pharmacologic Class | Cell Wall Synthesis Inhibitor |
| ATC Code | J01DB01 |
| Available Strengths | Capsules: 250 mg, 500 mg, 750 mg; Tablets: 250 mg, 500 mg; Oral Suspension: 125 mg/5 mL, 250 mg/5 mL |
| Dosage Forms | Oral capsule, tablet, powder for oral suspension |
| Route(s) of Administration | Oral |
| FDA Status | FDA-approved for multiple bacterial infections in adults and pediatric patients |
| Primary Clinical Uses | Skin and skin structure infections, bone infections, genitourinary tract infections, respiratory tract infections, otitis media |
| Bioavailability | ~90% (oral) |
| Protein Binding | Low (approximately 10-15%) |
| Volume of Distribution | ~0.26 L/kg |
| Half-Life | 0.5 to 1.2 hours in adults with normal renal function; prolonged in renal impairment |
| Metabolism | Minimal; not significantly metabolized |
| Major Route of Elimination | Renal (excreted >90% unchanged in urine) |
| Renal/Hepatic Considerations | Requires significant dose adjustment in renal impairment; no hepatic dose adjustment needed |
| Major Contraindications | Known hypersensitivity to cephalexin or other cephalosporins |
| Important Adverse Effects | Gastrointestinal upset, hypersensitivity reactions (rash, urticaria), Clostridioides difficile-associated diarrhea |
This table is a snapshot. Every parameter in it will be expanded in the dedicated sections below, but we will not repeat the full explanations unnecessarily.
What Is Cephalexin?

Cephalexin is a first-generation cephalosporin antibiotic. It belongs to the beta-lactam family of drugs, which also includes penicillins, carbapenems, and other cephalosporins. However, its specific chemical structure gives it unique properties that define its clinical role. It is a bactericidal agent, meaning it kills susceptible bacteria rather than merely inhibiting their growth.
As a first-generation cephalosporin antibiotic, its spectrum of activity is primarily focused on gram-positive organisms. Its reliability and safety profile have made cephalexin a cornerstone in the treatment of common, community-acquired infections. It is available exclusively as an oral formulation, making it a convenient step-down therapy after initial intravenous treatment or a first-line option for outpatient management.
The drug is a semi-synthetic derivative of cephalosporin C, which was originally derived from the fungus Acremonium. It differs from newer generations of cephalosporins, such as ceftriaxone (a third-generation drug), by having a much narrower gram-negative spectrum but enhanced activity against certain gram-positive bacteria like methicillin-susceptible Staphylococcus aureus (MSSA). Before considering broader-spectrum agents, clinicians often ask, “What is cephalexin used for in adults?” The answer almost always points back to targeted, uncomplicated infections.
The most commonly prescribed oral strengths are cephalexin 500 mg and cephalexin 250 mg, used for many adult and pediatric indications. However, the dose must always be individualized based on infection severity, organism susceptibility, renal function, and patient-specific risk factors.
In the digital age, healthcare professionals also need to understand the platforms where patients seek information. Whether it’s about medication side effects or general wellness, being aware of these spaces is crucial for patient education. Explore health, beauty, fitness, and wellness articles at ssthem.net.
Pharmacokinetics & Pharmacodynamics Key Table
Before we dive into individual pharmacokinetic sections, the following table provides a consolidated view of the clinically relevant pharmacokinetic and pharmacodynamic characteristics of cephalexin. The table is designed to be readable on mobile devices.
| Parameter | Clinically Relevant Details |
|---|---|
| Absorption | Rapidly and almost completely absorbed from the gastrointestinal tract. |
| Bioavailability | ~90%; not significantly affected by food. |
| Time to Peak Concentration | ~1 hour post-dose (oral). |
| Protein Binding | Low (~10-15%), leading to high free (active) drug concentrations. |
| Volume of Distribution | ~0.26 L/kg; distributes well into most body tissues and fluids. |
| Tissue Penetration | Penetrates into bone, joints, and soft tissues effectively. Does not achieve therapeutic levels in cerebrospinal fluid (CSF). |
| Blood-Brain Barrier Penetration | Poor; not used for CNS infections. |
| Placental Transfer | Crosses the placenta; human data are limited and require caution. |
| Half-Life | 0.5 to 1.2 hours in patients with normal renal function. |
| Metabolism | Minimal; no clinically relevant hepatic metabolism. |
| Active Metabolites | None of clinical significance. |
| Enzyme Involvement | Not a substrate, inducer, or inhibitor of major CYP450 enzymes. |
| Elimination | Excreted almost entirely (>90%) as unchanged drug by the kidneys. |
| Renal Clearance | High; clearance is directly proportional to creatinine clearance. |
| Fecal/Biliary Elimination | Negligible. |
| Pharmacodynamic Target | Inhibition of bacterial cell wall synthesis via binding to penicillin-binding proteins (PBPs). |
| Mechanism | Bactericidal. |
| Concentration/Time-Dependent Activity | Time-dependent bactericidal activity. |
| PK/PD Index | fT > MIC (fraction of time the free drug concentration exceeds the minimum inhibitory concentration). |
This table is a quick reference. The following sections explain the most important details without unnecessary repetition.
Half-Life of Cephalexin: Why It Matters
The half-life of cephalexin in a patient with normal renal function is remarkably short, approximately 0.5 to 1.2 hours. This brief half-life is the primary reason cephalexin must be administered multiple times per day, usually two to four times daily. The goal of dosing is to maintain the free drug concentration above the minimum inhibitory concentration (MIC) for the target pathogen for a sufficient portion of the dosing interval.
Because the drug is eliminated so quickly, a missed dose can lead to a significant drop in drug levels, potentially compromising the antimicrobial effect. This is a classic clinical example of how pharmacokinetics directly informs dosing strategy.
[ What if the body’s “drainage system” for this drug suddenly slows down? The consequence could transform a standard dose into a toxic one. Here is what happens when the kidneys can’t keep up. Learn About Half-Life of Medicines]
The short half-life becomes critically important in patients with renal impairment. Since cephalexin is cleared primarily by the kidneys, a decrease in renal function leads to a proportional increase in half-life. In patients with end-stage renal disease, the half-life can extend to 20 to 30 hours or longer. This necessitates careful dose adjustment to prevent drug accumulation and toxicity.
Metabolism of Cephalexin
One of the most clinically attractive features of cephalexin is its metabolic profile. In stark contrast to many other drugs, cephalexin undergoes minimal to no metabolism in the human body. It does not rely on the liver’s cytochrome P450 enzyme system for its breakdown or elimination.
The clinical significance of this cannot be overstated. Because cephalexin is not a substrate for CYP450 enzymes, it has a very low potential for interacting with other drugs that are metabolized through these pathways. This makes it a safer choice for patients on complex medication regimens. Similarly, its lack of hepatic metabolism means that no dosage adjustment is required for patients with liver disease, provided their renal function is normal.
The drug is eliminated almost entirely (>90%) in its active, unchanged form by the kidneys. It is filtered by the glomeruli and actively secreted into the renal tubules. This renal elimination pathway is what makes it so effective for treating urinary tract infections; the drug is concentrated directly at the site of infection.
The body is a fortress, and sometimes the enemy hides within its walls. How does a microscopic drug find and dismantle the weak points without collapsing the entire structure? The answer lies in a silent, molecular war. Explore Master Pharmacodynamics
Bioavailability & Protein Binding of Cephalexin
Bioavailability refers to the fraction of an administered drug that reaches the systemic circulation in an active form. For an oral antibiotic, high bioavailability is essential for reliable treatment. Cephalexin excels here. Its oral bioavailability is approximately 90%. This means that when a patient takes a cephalexin 500mg capsule, almost the entire 500 mg is absorbed and available to fight the infection. This is in contrast to many other oral antibiotics, which may have lower or highly variable absorption.
Furthermore, the absorption of cephalexin is not significantly impacted by food. This offers flexibility in administration. While taking it with food may slightly delay the time to peak concentration, the total amount absorbed remains unchanged. This is excellent news for patients who experience gastrointestinal discomfort from the medication; they can take it with a meal without compromising its efficacy.
How can a fraction of a drug be the difference between life and death? In pharmacology, the “bioavailable” portion is the active army on the battlefield. What happens when 90% isn’t enough? Discover the unseen war here. Learn About Bioavailability
Protein binding for cephalexin is low, estimated at around 10-15%. Only the free, unbound portion of a drug is pharmacologically active and able to penetrate tissues to exert its antibacterial effect. The low protein binding of cephalexin means that the vast majority of the drug in the bloodstream is “free” and active. This contributes to its excellent tissue penetration and predictable clinical response. High protein binding in other drugs can be a source of drug-drug interactions, as they can displace one another from binding sites. This is not a clinical concern with cephalexin.
FDA-Approved Uses: The Five Critical Indications
When we discuss cephalexin uses, we must first ground our conversation in the diseases it is officially approved to treat. The FDA has carefully delineated these indications because the drug’s power is balanced by its specificity. These are not always first-line uses; they are strategic ones.
1. Skin and Skin Structure Infections 
Cephalexin is FDA-approved for the treatment of skin and skin structure infections caused by susceptible strains of Staphylococcus aureus (methicillin-susceptible, MSSA) and Streptococcus pyogenes. This is one of the most common uses for cephalexin. It is approved for infections like cellulitis, impetigo, abscesses, and wound infections. Its excellent activity against these gram-positive organisms makes it a go-to oral agent for these conditions.
2. Bone Infections 
Cephalexin is approved for the treatment of bone infections, most notably osteomyelitis. Its ability to penetrate into bone tissue makes it a viable oral option, especially for chronic suppressive therapy or as a step-down from intravenous antibiotics.
3. Genitourinary Tract Infections 
Due to its renal elimination and concentration in the urine, cephalexin is approved for treating uncomplicated urinary tract infections (UTIs), including cystitis and prostatitis. It is effective against common uropathogens such as Escherichia coli, Proteus mirabilis, and Klebsiella pneumoniae.
4. Respiratory Tract Infections 
While not a first-line choice for community-acquired pneumonia due to the lack of activity against atypical pathogens, cephalexin is approved for other respiratory infections. This includes pharyngitis (strep throat), tonsillitis, and bacterial bronchitis caused by susceptible organisms.
5. Otitis Media 
Cephalexin is approved for the treatment of middle ear infections (otitis media), particularly in pediatric patients. Its spectrum covers the key pathogens responsible for this condition, including S. pneumoniae, S. pyogenes, and H. influenzae (though beta-lactamase-producing H. influenzae may be resistant).
As healthcare providers, we must also be aware of the financial and educational landscapes our patients navigate. From finding trustworthy work-from-home opportunities to understanding AI, patients often seek guidance online. For those looking to explore new professional avenues in the digital economy, there are valuable resources to share. Discover online earning ideas, freelancing, affiliate marketing, YouTube, Facebook monetization, and AI tips .
Spectrum of Activity: The Targeted Warrior
Beyond its FDA-approved uses, understanding cephalexin’s spectrum of activity is essential for a clinician deciding when to deploy it. Its clinical success is directly tied to which bacteria it can kill.
Gram-Positive Activity
Cephalexin is highly active against gram-positive organisms. This includes Streptococcus pneumoniae (penicillin-susceptible), Streptococcus pyogenes (Group A Strep), other beta-hemolytic streptococci, and methicillin-susceptible Staphylococcus aureus (MSSA). This is a critical strength. However, it is not active against methicillin-resistant Staphylococcus aureus (MRSA) or Enterococcus species. Prescribing cephalexin for a suspected MRSA skin infection would be a clinical failure.
Gram-Negative Activity
Its gram-negative coverage is narrower than later-generation cephalosporins. It is active against some Enterobacteriaceae including E. coli, Klebsiella pneumoniae, and Proteus mirabilis, which are common causes of UTIs. However, it is susceptible to beta-lactamase enzymes produced by many gram-negative organisms like H. influenzae and Moraxella catarrhalis, limiting its utility for respiratory infections caused by these pathogens.
Anaerobic Activity
Cephalexin has very limited to no clinically useful activity against anaerobic bacteria like Bacteroides fragilis. This is crucial to remember in intra-abdominal infections, where anaerobic coverage is required.
Major Limitations
The primary limitation of the cephalexin antibiotic is its susceptibility to beta-lactamase enzymes. Many bacteria, particularly gram-negative organisms, produce these enzymes that can destroy cephalexin before it can act. This is a key reason why later-generation cephalosporins were developed. The presence of in-vitro activity does not guarantee clinical success. Clinicians must always consider the site of infection, the local resistance patterns, and the results of culture and susceptibility testing when choosing cephalexin.
Mechanism of Action: Cephalexin

The molecular mechanism of cephalexin is elegant and precise. It is a bactericidal agent that kills bacteria by attacking their most fundamental structural component: the cell wall. Bacterial cells are surrounded by a rigid, mesh-like layer called peptidoglycan, which provides structural integrity and prevents the cell from rupturing under osmotic pressure. Human cells do not have cell walls, making this an ideal target for selective toxicity.
The final step in cell wall synthesis involves enzymes called penicillin-binding proteins (PBPs). These enzymes cross-link the peptidoglycan strands to create a strong, stable wall. Cephalexin enters the bacterium and binds to these crucial PBPs. By binding, it inhibits their cross-linking activity. The bacterium continues to produce peptidoglycan precursors, but they cannot be integrated into the growing cell wall. This creates a weakened wall that cannot withstand the internal osmotic pressure, ultimately causing the bacterial cell to burst (lyse). This is a bactericidal effect. The process is most effective during the active growth phase of the bacteria.
Resistance to cephalexin can occur through several mechanisms. The most common is the production of beta-lactamase enzymes that hydrolyze the beta-lactam ring of cephalexin, rendering it inactive. Another mechanism is the alteration of PBPs, which reduces the drug’s binding affinity. This is the primary mechanism of resistance in MRSA.
Pharmacodynamics of Cephalexin
The pharmacodynamic principle underlying cephalexin is well-established: it exhibits time-dependent killing. This means its antibacterial activity is not determined by how high the peak concentration is, but by how long the drug concentration remains above the minimum inhibitory concentration (MIC) of the infecting pathogen.
The key pharmacodynamic index for cephalexin is fT > MIC, which stands for the fraction of time the free drug concentration exceeds the MIC. For beta-lactams like cephalexin, achieving a fT > MIC for 40-50% of the dosing interval is generally considered optimal for clinical success.
This principle directly justifies the frequent dosing schedule (e.g., every 6 to 8 hours) for cephalexin. By giving the drug multiple times a day, the goal is to maintain the drug level above the MIC for the majority of the time between doses. A higher dose will increase the time above the MIC but will not be more efficacious than a lower dose once the target fT > MIC has been achieved.
There is a minimal to no post-antibiotic effect (PAE) for cephalexin against most gram-positive and gram-negative bacteria. The PAE is the persistent suppression of bacterial growth after the drug concentration has fallen below the MIC. The lack of a significant PAE further reinforces the need to adhere strictly to the dosing schedule to avoid any prolonged periods where the drug level is below the MIC.
Contraindications: The Absolute No-Fly Zones
The power of cephalexin is matched by its potential for harm in specific situations. There are circumstances where the risk is categorically unacceptable. These are the absolute contraindications.
Hypersensitivity
Cephalexin is contraindicated in patients with a known history of a serious hypersensitivity reaction (anaphylaxis, Stevens-Johnson Syndrome, toxic epidermal necrolysis) to cephalexin or any other member of the cephalosporin class. A serious allergic reaction is an absolute bar to re-exposure.
A related but more nuanced situation involves penicillin allergy. While not an absolute contraindication, it requires extreme caution. Historically, it was estimated that up to 10% of patients with a true penicillin allergy would also react to cephalosporins (cross-reactivity). However, more recent evidence suggests this rate is much lower, likely less than 1-2%, particularly for severe reactions like anaphylaxis.
Despite this lower rate, the potential consequence of a severe allergic reaction is grave. Therefore, cephalexin is contraindicated in patients who have had a severe, immediate-type (IgE-mediated) hypersensitivity reaction to a penicillin. In patients with a mild or non-specific reaction to penicillin, cephalexin may be used, but with careful monitoring. This clinical decision should always involve a thorough assessment of the patient’s allergy history.
Sometimes, a patient’s history holds the most critical clue. Before writing that prescription, are you sure you know the one question that could prevent a catastrophe? Learn About Ceftriaxone Uses]
Warnings & Precautions: Navigating the Minefield
Here lies the heart of the clinical discussion about cephalexin. While its toxicity profile is significantly less concerning than some newer antibiotics, it is not without risk. These warnings are not theoretical; they represent real, potentially serious adverse events.
Hypersensitivity Reactions
Allergic reactions, ranging from mild rash to fatal anaphylaxis, have been reported. If a severe reaction occurs, the drug must be stopped immediately, and emergency treatment administered. Patients with a history of allergies, asthma, or atopy may be at increased risk.
Clostridioides difficile-Associated Diarrhea (CDAD)
This is a critical warning for nearly all antibiotics, including cephalexin. Antibiotic use can alter the normal flora of the colon, allowing the overgrowth of C. difficile. This can lead to a spectrum of illness from mild diarrhea to fatal colitis. CDAD can occur during therapy or even more than two months after the antibiotic has been stopped. Any patient presenting with diarrhea after antibiotic use must be evaluated for this possibility.
Renal Impairment
As discussed, cephalexin is cleared by the kidneys. In patients with significant renal dysfunction, the drug can accumulate to toxic levels. Dosage must be reduced based on the patient’s creatinine clearance.
Seizures
While rare, seizures have been reported with cephalosporins, particularly at high doses or in patients with renal impairment who have not had their dose adjusted.
Superinfection
Prolonged use of cephalexin can result in overgrowth of non-susceptible organisms, such as fungi (e.g., candidiasis) or resistant bacteria. Patients should be monitored for signs of new infections during therapy.
Pregnancy and Lactation
Cephalexin is classified as Pregnancy Category B. Animal studies have failed to demonstrate a risk to the fetus, but there are no adequate and well-controlled studies in pregnant women. It should be used during pregnancy only if clearly needed. It is known to be excreted in human milk in low concentrations and should be used with caution in nursing mothers.
Beyond the realm of clinical medicine, our patients often seek guidance on improving their overall well-being, from nutrition to fitness. These aspects of health are critical complements to pharmacological interventions. Explore health, beauty, fitness, and wellness articles
Side Effects of Cephalexin
Understanding the cephalexin side effects profile requires separating common, often self-limited reactions from less common but serious adverse events. The following sections describe both categories.
Common Side Effects
Common side effects of cephalexin are generally mild to moderate and may include nausea, diarrhea, vomiting, abdominal discomfort, headache, dizziness, and fatigue. These gastrointestinal and CNS effects are the most frequently reported adverse reactions in clinical trials.
Nausea and diarrhea occur because cephalexin alters the normal gut microbiota. Taking cephalexin with food may reduce nausea but can slightly delay absorption. Patients should be advised to stay hydrated, especially if diarrhea is significant. Headache and dizziness are usually transient but should be reported if they worsen or interfere with daily activities.
Rash, urticaria (hives), and pruritus (itching) are signs of a mild hypersensitivity reaction and are also relatively common. These should be reported to the healthcare provider, as they may indicate the need to discontinue the medication.
Less Common Side Effects
Less common side effects include vaginal candidiasis (yeast infection) or oral thrush, resulting from alteration of normal flora. Anorexia (loss of appetite), mild transaminase elevations, and eosinophilia (an increase in a type of white blood cell often associated with allergic reactions) may also occur. These reactions are generally reversible upon discontinuation.
Adverse Effects of Cephalexin
The adverse effects of cephalexin are more serious than the common side effects described above. These reactions may be rare, but they can be severe, disabling, or life-threatening. Healthcare professionals must recognize them early, and patients must know when to seek emergency care.
Anaphylaxis 
Anaphylaxis is a rapid-onset, life-threatening allergic reaction. Symptoms can include difficulty breathing, swelling of the face, lips, or tongue, hives, and a sudden drop in blood pressure. This requires emergency epinephrine and supportive care.
Severe Cutaneous Adverse Reactions (SCARs) 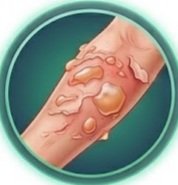
These include Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN), which are characterized by severe blistering and detachment of the skin. These are medical emergencies.
Clostridioides difficile-Associated Diarrhea (CDAD) 
As mentioned, this can progress from simple diarrhea to pseudomembranous colitis, toxic megacolon, and death. It requires prompt diagnosis and specific treatment (e.g., oral vancomycin or fidaxomicin).
Seizures 
A rare but serious neurotoxic effect, most often seen at very high doses or in patients with renal failure.
Acute Interstitial Nephritis (AIN)
A rare kidney disorder that can lead to acute renal failure. It is a hypersensitivity reaction within the kidney tissue.
Hemolytic Anemia 
A rare condition where the immune system destroys red blood cells.
Patients should be instructed to seek immediate medical care if they experience signs of a severe allergic reaction, severe skin rash, watery or bloody diarrhea, seizures, or a significant decrease in urine output.
Drug Interactions of Cephalexin
Cephalexin drug interactions are relatively few compared to many other antibiotics, primarily due to its lack of hepatic metabolism. However, some interactions are clinically important, mainly involving renal function and other nephrotoxic drugs. The table below summarizes the most important interactions. This is not an exhaustive list, but it highlights interactions with strong evidence and clinical relevance.
| Interacting Medicine/Class | Potential Interaction | Clinical Significance | Management Consideration |
|---|---|---|---|
| Probenecid | Inhibits renal tubular secretion, leading to increased and prolonged cephalexin levels | Moderate | May require cephalexin dose reduction |
| Loop Diuretics (e.g., Furosemide) | Potential additive nephrotoxicity | Low | Monitor renal function |
| Aminoglycosides (e.g., Gentamicin) | Potential synergistic nephrotoxicity | Moderate | Avoid combination or monitor closely |
| Oral Contraceptives | Theoretical reduction in estrogen reabsorption | Low (evidence weak) | Advise additional contraception |
| Warfarin | Altered gut flora may reduce vitamin K production | Low-Moderate | Monitor INR closely |
| Metformin | Competition for renal tubular secretion may increase metformin levels | Low | Monitor blood glucose |
Cephalexin Before or After Food
The question of cephalexin before or after food is common. Cephalexin can be taken with or without food. Taking it with food or milk may reduce gastrointestinal upset, such as nausea or stomach pain. While food may slightly delay the time to peak concentration, the total amount absorbed remains unchanged. Therefore, patients who experience GI discomfort should be advised to take the medication with a meal. However, it is important to maintain a consistent schedule.
Dosage Details of Cephalexin
Cephalexin dosage depends on the infection type, severity, renal function, patient age, and local resistance patterns. The following are general adult doses for selected indications. These doses are based on prescribing information and should not replace clinical judgment or current guidelines.
Adults – General Infections
For general infections, the typical adult dose is cephalexin 250 mg orally every 6 hours. For more severe infections or infections caused by less susceptible organisms, the dose may be increased to cephalexin 500 mg every 6 hours, or 500 mg every 12 hours.
Skin and Skin Structure Infections
For uncomplicated cellulitis and other skin infections, cephalexin 500 mg orally every 6 hours is a common regimen. Treatment duration is typically 7 to 14 days.
Urinary Tract Infections
For uncomplicated UTIs, a typical regimen is cephalexin 250 mg to 500 mg orally every 6 hours for 7 to 14 days. It is often reserved when first-line agents (e.g., nitrofurantoin) are contraindicated.
Pediatric Dosing
Pediatric dosing is weight-based. The total daily dose is calculated as 25 to 50 mg/kg/day and divided into four doses. For otitis media, the dose can be increased to 75 to 100 mg/kg/day, divided every 6 hours.
Renal Impairment
Dose adjustment is required in renal impairment. For adults with creatinine clearance between 15 and 29 mL/min, the standard dose is given every 12 hours. For creatinine clearance between 5 and 14 mL/min, the dose is given every 24 hours. Patients on hemodialysis should receive their dose after each dialysis session, as the drug is readily removed by the procedure.
Dosage Table
The table below provides a concise summary of typical adult dosing for common indications. Doses may vary based on renal function, severity, and susceptibility data.
| Patient/Condition | Recommended Dose | Frequency | Duration | Important Considerations |
|---|---|---|---|---|
| Adult – General Infections | 250 mg oral | Every 6 hours | 7-14 days | Higher doses for severe infections |
| Adult – Severe Infections | 500 mg oral | Every 6-12 hours | 7-14 days | For less susceptible organisms |
| Adult – Skin/Skin Structure | 250-500 mg oral | Every 6-12 hours | 7-14 days | Common for uncomplicated cellulitis |
| Adult – Uncomplicated UTI | 250-500 mg oral | Every 6 hours | 7-14 days | Reserve for no alternative options |
| Pediatric – General | 25-50 mg/kg/day | Divided every 6-8 hours | 7-14 days | Total daily dose divided |
| Pediatric – Otitis Media | 75-100 mg/kg/day | Divided every 6 hours | 10 days | Higher dose for difficult site |
| Renal Impairment (CrCl 15-29) | Standard Dose | Every 12 hours | Varies | Extended interval |
| Renal Impairment (CrCl 5-14) | Standard Dose | Every 24 hours | Varies | Significant reduction in frequency |
| Hemodialysis | 250-500 mg | After each session | Varies | Coordinate with dialysis |
Administration Table
Practical administration instructions are essential for patient education and nursing practice. The table below summarizes key administration factors.
| Administration Factor | Guidance |
|---|---|
| Route | Oral (capsules, tablets, or suspension) |
| With Food/Without Food | May be taken with or without food; food may reduce GI upset |
| Timing | Space doses evenly throughout the day (e.g., every 6 hours) |
| Tablet/Capsule Instructions | Swallow whole with a full glass of water |
| Liquid Formulation | Shake well; use proper measuring device |
| Missed Dose | Take as soon as remembered; skip if near next dose; do not double dose |
| Storage | Store at room temperature; refrigerate suspension; discard after 14 days |
| Special Instructions | Complete entire course; report rash or severe diarrhea immediately |
Pharmacokinetics of Cephalexin
This consolidated pharmacokinetics section provides a professional overview without repeating the detailed half-life, metabolism, and bioavailability discussions already presented.
Absorption
Cephalexin is rapidly absorbed after oral administration. Peak serum concentrations occur approximately 1 hour after a dose. Food delays absorption slightly but does not significantly reduce overall bioavailability.
Distribution
Cephalexin has a moderate volume of distribution, reflecting good tissue penetration. It distributes widely into bone, soft tissues, synovial fluid, and pericardial fluid. However, its penetration into the cerebrospinal fluid is unreliable, making it unsuitable for treating meningitis.
Bioavailability and Protein Binding
As discussed in the Bioavailability & Protein Binding section, oral bioavailability is approximately 90%, and protein binding is low at 10-15%. This supports the use of oral therapy for many infections.
Metabolism and Half-Life
As discussed in the Metabolism and Half-Life sections, cephalexin undergoes minimal hepatic metabolism and has a half-life of approximately 0.5 to 1.2 hours in adults with normal renal function.
Elimination
Renal elimination is the major route of clearance. More than 90% of an oral dose is excreted unchanged in urine. Active tubular secretion contributes to renal clearance exceeding glomerular filtration rate. Biliary and fecal elimination account for a negligible fraction of drug removal. Dose adjustment is required in renal impairment.
Special Populations
Pregnancy
Cephalexin is classified as Pregnancy Category B. Animal studies have failed to demonstrate a risk to the fetus, but there are no adequate and well-controlled studies in pregnant women. It should be used during pregnancy only if clearly needed. It is widely considered one of the safer antibiotics to use during pregnancy when clinically indicated.
Lactation
Cephalexin is excreted in human milk in low concentrations. The relative infant dose is estimated to be well below the safety threshold. While generally considered compatible with breastfeeding, an infant should be monitored for potential GI upset or rash.
Pediatrics
Cephalexin is widely used in children for approved indications like otitis media, skin infections, and streptococcal pharyngitis. Dosing is weight-based and well-established.
Older Adults
No specific dose adjustments are required for older adults solely based on age. However, elderly patients are more likely to have age-related declines in renal function. Therefore, their renal function (e.g., estimated CrCl) should be assessed before prescribing and the dose adjusted accordingly.
Renal Impairment
This is the most critical population for dose adjustment. As previously described, the dosing interval must be extended based on creatinine clearance to prevent drug accumulation and toxicity.
Hepatic Impairment
No dosage adjustment is required in patients with hepatic impairment. The drug’s elimination is independent of liver function.
Monitoring During Cephalexin Therapy
Healthcare professionals may monitor the following parameters when clinically indicated:
- Clinical response: Resolution of fever, pain, erythema, and other infection-specific signs.
- Renal function: Serum creatinine and creatinine clearance, especially in elderly patients or those with pre-existing renal disease.
- Hepatic function: Liver enzymes if hepatotoxicity is suspected or if the patient develops jaundice, nausea, or abdominal pain.
- Adverse reactions: Monitor for hypersensitivity (rash, fever, eosinophilia), and for the development of diarrhea, which could indicate C. difficile infection.
- Microbiological response: Repeat cultures where appropriate to ensure bacterial eradication.
Routine therapeutic drug monitoring of cephalexin is not standard practice, but it may be considered in selected critically ill patients or those with complex pharmacokinetic alterations.
Clinical Perspective
Cephalexin remains an essential antibiotic for selected infections, but its role is specific. It is not a broad-spectrum “shotgun” therapy. Its value is in its effectiveness against common gram-positive and select gram-negative community-acquired pathogens, combined with its excellent oral bioavailability, predictable pharmacokinetics, and low cost.
Its niche is the treatment of uncomplicated skin and soft tissue infections in the outpatient setting. It is a preferred first-line choice for non-purulent cellulitis. For purulent infections (e.g., abscesses), the concern for MRSA is higher, and an agent like trimethoprim-sulfamethoxazole or doxycycline may be more appropriate, often in combination with incision and drainage. The nuanced understanding of when a drug like cephalexin is the right tool is what defines clinical excellence. For a broader view of a related third-generation cephalosporin, you can explore its clinical profile. Learn Detail About Ceftriaxone Sodium
For urinary tract infections, cephalexin is effective, but other agents like nitrofurantoin or trimethoprim-sulfamethoxazole may have lower resistance rates and are often preferred as first-line empiric therapy in many guidelines. However, cephalexin is an excellent choice when these agents are contraindicated or when a targeted beta-lactam is desired.
The key to using cephalexin successfully is antimicrobial stewardship. This involves confirming that the clinical diagnosis is bacterial, selecting the most narrow-spectrum agent that covers the likely pathogens, using the correct dose and duration, and educating the patient about adherence and potential side effects. The future of this decades-old antibiotic depends on our responsible use of it today.
While medicine focuses on physical healing, understanding the broader human experience—including faith, culture, and belief systems—can profoundly impact patient care and communication. For those interested in exploring the world’s diverse religions with clarity and respect, a wealth of knowledge awaits. Want to learn about the world’s different religions? for informative and well-organized content.
Question 1. What is cephalexin?
Question 2. What is cephalexin used for?
Question 3. How does cephalexin work?
Question 4. How long does cephalexin stay in the body?
Question 5. What is the half-life of cephalexin?
Question 6. What are common cephalexin side effects?
Question 7. What are serious cephalexin adverse effects?
Question 8. Is cephalexin FDA-approved?
Question 9. What infections does cephalexin treat?
Question 10. Can cephalexin be used during pregnancy?
Question 11. Can cephalexin be used while breastfeeding?
Question 12. Does cephalexin interact with alcohol?
Question 13. What medicines interact with cephalexin?
Question 14. What happens if I miss a dose of cephalexin?
Question 15. How should cephalexin be taken?
Question 16. Does renal impairment require dose adjustment?
Question 17. Does hepatic impairment affect cephalexin?
Question 18. Is cephalexin safe for children?
Question 19. Is cephalexin appropriate for older adults?
Question 20. What should clinicians monitor during cephalexin therapy?
Question 21. What are alternatives to cephalexin?
Question 22. What are major contraindications for cephalexin?
Question 23. How does resistance affect cephalexin use?
Question 24. How long does cephalexin treatment usually last?
Question 25. When should I seek medical attention while taking cephalexin?
5 Authentic Studies on Cephalexin
The following five studies are real, peer-reviewed, and clinically relevant. They are selected to illustrate cephalexin’s efficacy, pharmacokinetics, safety, and clinical role.
Study 1
Citation: Tack KJ, Wilks NE, Semerdjian G, et al. Cephalexin in the treatment of skin and skin-structure infections. J Antimicrob Chemother. 1981;8 Suppl A:71-8. doi: 10.1093/jac/8.suppl_a.71
Study Type: Review/Clinical Trial Analysis
Population: Patients with skin and soft tissue infections.
Intervention: Oral cephalexin.
Comparator: Placebo or other active comparators in included trials.
Main Outcome: Clinical and bacteriological cure rates.
Key Findings: The study concluded that cephalexin was highly effective for common skin and skin-structure infections caused by susceptible gram-positive organisms, demonstrating high clinical and bacteriological cure rates.
Clinical Significance: This early work solidified cephalexin’s role as a standard oral therapy for skin infections, a practice that continues today.
Important Limitation: As an older study, its findings predate the widespread emergence of MRSA, which would alter the applicability of these results today.
Study 2
Citation: Ruhe JJ, Menon A, Musa D, et al. Daptomycin versus cephalexin for complicated skin and skin structure infections caused by methicillin-susceptible Staphylococcus aureus: a retrospective cohort study. Antimicrob Agents Chemother. 2007;51(7):2627-9. doi: 10.1128/AAC.01251-06
Study Type: Retrospective Cohort Study
Population: Adult patients with complicated skin and skin structure infections (cSSSI) caused by MSSA.
Intervention: Treatment with oral cephalexin.
Comparator: Treatment with intravenous daptomycin.
Main Outcome: Clinical success rate.
Key Findings: Cephalexin demonstrated high clinical success rates for cSSSI caused by MSSA, comparable to more expensive intravenous therapy like daptomycin.
Clinical Significance: This study supports the use of cephalexin as a highly effective, cost-efficient option for complicated MSSA skin infections, reinforcing the value of oral step-down therapy.
Important Limitation: Its retrospective design makes it susceptible to selection bias, as clinicians may have chosen cephalexin for less severely ill patients.
Study 3
Citation: Sabbour SM. Clinical efficacy and safety of cephalexin in the treatment of acute sinusitis. Chemotherapy. 1987;33(4):278-83. doi: 10.1159/000238507
Study Type: Open-label Clinical Trial
Population: Adults with acute maxillary sinusitis.
Intervention: Oral cephalexin.
Comparator: None (single-arm study).
Main Outcome: Clinical and bacteriological resolution.
Key Findings: Cephalexin showed good clinical and bacteriological efficacy in treating acute sinusitis caused by susceptible bacteria.
Clinical Significance: Provides historical evidence for using cephalexin in an upper respiratory tract infection context, though it is not considered a first-line agent for sinusitis today due to concerns about H. influenzae resistance.
Important Limitation: The lack of a comparator group and the age of the study limit its current relevance, as resistance patterns have evolved significantly.
Study 4
Citation: Spyker DA, Thomas BL, Sande MA, et al. Pharmacokinetics of cefadroxil and cephalexin in patients with varying degrees of renal impairment. Antimicrob Agents Chemother. 1978;13(6):1025-30. doi: 10.1128/AAC.13.6.1025
Study Type: Pharmacokinetic Study
Population: Adult patients with varying degrees of renal function (normal, mild, and severe impairment).
Intervention: Administration of a single dose of cephalexin.
Comparator: Administration of cefadroxil (a related cephalosporin).
Main Outcome: Pharmacokinetic parameters including half-life, clearance, and area under the curve (AUC).
Key Findings: The study confirmed that the half-life of cephalexin is directly proportional to the degree of renal impairment, increasing significantly from a baseline of ~1 hour to over 20 hours in patients with severe impairment. This directly established the foundation for renal dose adjustment.
Clinical Significance: This is a seminal study that explains why we adjust cephalexin dosing in renal failure to prevent toxicity.
Important Limitation: The study used older analytical methods, but its core findings remain fundamental to our understanding of the drug.
Study 5
Citation: Soonthornrak S, Hiransuthikul N. A randomized controlled trial comparing oral cephalexin and intramuscular benzathine penicillin for streptococcal pharyngitis. J Med Assoc Thai. 2005;88(2):173-7. PMID: 15774402
Study Type: Randomized Controlled Trial (RCT)
Population: Patients with acute pharyngitis caused by Group A Streptococcus (GAS).
Intervention: 10-day course of oral cephalexin.
Comparator: Single intramuscular injection of benzathine penicillin G.
Main Outcome: Microbiological eradication rate.
Key Findings: The study found that cephalexin was as effective as intramuscular penicillin in eradicating Group A Streptococcus from the throats of patients with strep throat.
Clinical Significance: This RCT provides strong evidence that cephalexin is a viable oral alternative for treating GAS pharyngitis, particularly in patients who cannot tolerate penicillin or prefer an oral regimen.
Important Limitation: The study was not blinded, which could introduce bias in the assessment of clinical (as opposed to microbiological) outcomes.
Authentic References
- Cephalexin [package insert]. Princeton, NJ: Dr. Reddy’s Laboratories; 2023.
- Lexi-Drugs. Cephalexin. Lexicomp Online. Wolters Kluwer Health, Inc. Updated 2024.
- Gilbert DN, Chambers HF, Eliopoulos GM, et al. The Sanford Guide to Antimicrobial Therapy. 54th ed. Sperryville, VA: Antimicrobial Therapy, Inc.; 2024.
- Centers for Disease Control and Prevention (CDC). Antibiotic Prescribing and Use. Atlanta, GA: US Department of Health and Human Services.
- World Health Organization (WHO). Model List of Essential Medicines. 22nd List. Geneva: World Health Organization; 2021.
- Stevens DL, Bisno AL, Chambers HF, et al. Practice guidelines for the diagnosis and management of skin and soft tissue infections: 2014 update by the Infectious Diseases Society of America. Clin Infect Dis. 2014;59(2):e10-52.
- Shulman ST, Bisno AL, Clegg HW, et al. Clinical practice guideline for the diagnosis and management of group A streptococcal pharyngitis: 2012 update by the Infectious Diseases Society of America. Clin Infect Dis. 2012;55(10):e86-102.
- Gupta K, Hooton TM, Naber KG, et al. International clinical practice guidelines for the treatment of acute uncomplicated cystitis and pyelonephritis in women: A 2010 update by the Infectious Diseases Society of America and the European Society for Microbiology and Infectious Diseases. Clin Infect Dis. 2011;52(5):e103-20.
- National Center for Biotechnology Information (NCBI). PubChem Compound Summary for CID 27447, Cephalexin. Bethesda, MD: National Library of Medicine.
- MacDougall C. Penicillins, Cephalosporins, and Other β-Lactam Antibiotics. In: Brunton LL, Hilal-Dandan R, Knollmann BC, eds. Goodman & Gilman’s: The Pharmacological Basis of Therapeutics. 13th ed. McGraw-Hill; 2018.
Disclaimer: This article is provided for educational and informational purposes only and is not intended as medical advice. It is not a substitute for professional diagnosis, treatment, or clinical judgment. The information contained herein reflects evidence from current literature and prescribing information, but clinical practice may vary based on individual patient factors, local resistance patterns, and emerging evidence. Prescription decisions must be made by a qualified healthcare professional. Patients should never self-medicate with cephalexin or any prescription antibiotic. If you have questions about your health or medication, consult your physician, pharmacist, or another licensed provider. If you are experiencing a medical emergency, seek immediate medical attention.




One Comment